Kidney Stones

What are kidney stones? How do they form?

A kidney stone is a small mass that forms from crystallized substances in your kidney or, in some cases, one of your ureters (the tubes that connect the kidneys to the bladder). These chemicals aren’t able to dissolve in urine, so the crystals stick together and get larger, forming the stone. (Note: Stones that form in the ureters are called ureteral stones.)

Abstract image of kidney disease and kidney stones

You can be especially prone to kidney stones if you’re frequently dehydrated and there is less water to dissolve the substances. You can also develop them if your levels of the chemicals that crystallize to form stones are too high.

Kidney stones vary in size, shape, and color.
They are also made from different substances, depending on the type of stone.

Stones vary in texture and size. Some are smooth, while others have more jagged edges. Most stones are less than 5 mm in diameter (about 3/16 of an inch) and they usually pass on their own through urine. But sometimes, stones become larger (even as large as a golf ball) or have trouble passing through the urinary tract. If this happens, you’ll need treatment, which we’ll discuss below.

Other terms for kidney stones are renal stone disease, nephrolithiasis and urolithiasis. Why are there so many names for kidney stones? The other names are scientific names. Both the word “renal” and the prefix “nephro” mean “relating to the kidneys” and scientists may sometimes refer to kidney stones as renal calculi or nephroliths.

Who gets kidney stones?

The American Kidney Fund estimates that about 1 in 5 males and 1 in 14 females will get a kidney stone in their lifetime. Each year, about half a million people go to the emergency room because of kidney stones, the National Kidney Foundation reports.

People of all ages can get kidney stones.

What causes kidney stones?

Kidney stones form from substances found in your urine, like uric acid, calcium, oxalate, and cystine. You can get kidney stones if you have high levels of these substances in your system. But you might also get them if your body doesn’t make enough urine.

In either case, tiny crystals form and gradually get bigger, making a stone. Most of the time, stones just travel through your urinary tract and pass with your urine. But sometimes, they get stuck on the way and block urine flow.

What are the risk factors for kidney stones?

Here are some common risk factors for kidney stones:

Your previous health history. If you have had kidney stones in the past or if you’ve had gastric bypass surgery, you could be at higher risk.

Your family history. If you have an immediate family member – a parent, brother or sister – with a history of kidney stones, you’ll be more likely to develop them yourself.

Dehydration. When you become dehydrated, your body doesn’t produce as much urine and stone-forming substances have a harder time dissolving.

Bowel problems. Frequent diarrhea can make you dehydrated.

Your diet. High levels of calcium, salt, sugar, and animal protein can make you more susceptible to kidney stones. It’s possible that you’re consuming too much of these items in your diet. But it’s also possible that your body isn’t processing them as it should. Once we know more about your kidney stones, we can advise you on foods to choose and foods to avoid.

Health conditions. Obesity, abnormal growth of parathyroid glands (glands that produce a hormone that regulates levels of calcium and phosphorus in the body), and distal renal tubular acidosis (excess amounts of acid in the blood as a result of poor kidney function) are kidney stone risk factors.
Other health issues that can raise your risk for kidney stones are diabetes, polycystic kidney disease, arthritis, and gout.

Medications and supplements. For example, if you take calcium or vitamin C supplements, you might be more prone to kidney stones. If you make a list of the medications and supplements you take, we can review it with you.

How are kidney stones classified?

Six kidney stones in various sizes and textures
These kidney stones are all from the same person, but on different occasions. The bigger is 11 mm across. All came out the natural way, without surgery.

Kidney stones vary in size, shape, and color. They are also made from different substances, depending on the type of stone. Knowing of the type of kidney stone you have helps us treat it most effectively.

Calcium stones. Most kidney stones (about 80%) are made from either calcium oxalate or calcium phosphate. These can form if there’s too much calcium in your urine.

Uric acid stones. Uric acid is produced when your body breaks down compounds called purines, which are found in foods like dried beans, peas, and some meats and shellfish. When uric acid crystals accumulate, they can form a uric acid stone.

Struvite stones. Struvite stones (sometimes called “infection stones”) are more common in people who get frequent urinary tract infections (UTIs). Bacteria that cause UTIs disrupt the chemical balance in the urine. Struvite stones are sometimes called staghorns because they have a jagged appearance.

Cystine stones. This type of stone, made from an amino acid called cystine, is caused by a rare inherited condition called cystinuria. People with cystinuria have too much cystine in their urine.

Symptoms

Symptoms may be different depending on the type of stone you have, but some of the more typical symptoms are:

Back pain, kidney inflammation, man suffering from backache at home

Pain

You might have heard stories about pain associated with kidney stones because the pain can be intense, but it’s not always so. Usually pain occurs when urine can’t flow past the stone. You might feel pain in your back, side, abdomen, or groin. Pain can be mild or severe, and it often fluctuates.

Periods of severe pain are called renal colic. These episodes can last up to an hour.

We can help you manage the pain, but if it becomes unbearable and you are unable to reach us, don’t hesitate to head to the ER.

Some men feel pain in their testes or penis as the stone passes. Once the stone is passed, the pain stops.”

Blood in your urine (hematuria) or “sand.”

If you have blood in your urine, you might see a pink or reddish tint in the toilet. But it’s also possible that you won’t see anything different at all. Microhematuria (microscopic hematuria) occurs when the blood particles are too small to see with the naked eye.

You might also notice tiny stones in your urine. Urologists call the particles “gravel” or “sand.”

Urination changes

You might urinate more frequently or feel like you need to go to the bathroom more often, even if you don’t produce much or any urine. You could also have pain or a burning sensation when you urinate. Urine may be cloudy or have an odor.

Nausea. You might start vomiting.

Fever and chills. You may have these symptoms if your stone is related to a UTI.

It’s also possible for people with kidney stones to have no symptoms at all. In fact, some people have kidney stones for years without experiencing any problems.

Diagnosing kidney stones

When you come see us, we’ll start by taking a complete medical history. Be sure to tell us about your diet. That can give us some important clues. We’ll also ask about the medications you take and whether anyone in your family has had stones before.

Next, we’ll do some tests, which may include the following:

  • Urine tests and blood tests. Substances that form stones, like calcium and uric acid, may be present in your urine or blood.
  • Imaging tests. A CT scan (a “cat” scan – computed tomography) or an ultrasound can indicate the size, shape, and quantity of kidney stones.
  • Stone analysis. If you’ve had kidney stones before (and one has been saved), analyzing a previous stone might provide clues for your current situation.
  • Genetic tests. Some kidney stones are caused by inherited conditions, like cystinuria. Genetic tests might tell us if you are likely to develop kidney stones.

Kidney stone treatment

If your stone is small and your pain is mild, you might be able to manage your kidney stone at home. If it’s safe for you, we’ll recommend nonsteroidal anti-inflammatory drugs (NSAIDS) like ibuprofen or naproxen. We might also prescribe medication like tamsulosin (Flomax), which can help your stone pass by relaxing the ureter. This process can take a few weeks.

We might ask you to strain your urine when you’re home. If you catch the stone as it passes, save it and bring it to us for analysis. This will help us determine what type of stone it is.

If your stone is large or doesn’t pass on its own after 4 to 6 weeks, you’ll need more advanced treatment. You will likely have imaging tests and a urinalysis beforehand. These tests results help us choose the best treatment for you.

Ureteroscopy

This procedure is generally used to treat stones in your kidney or ureter. After you have received anesthesia, a thin tool called a ureteroscope is threaded through your urethra and bladder until it reaches the ureter or kidney. The ureteroscope offers doctors a better view of the stone. It can also remove the stone or break it into smaller pieces that can pass on their own.

Chances are, you’ll be able to go home the same day as your ureteroscopy and go back to your daily routine in two to three days.

After a ureteroscopy, you might have a temporary stent — a small tubelike structure — placed in your ureter to keep it open. The stent is usually removed about four to ten days after your procedure.

Shock wave lithotripsy (SWL)

SWL uses shock waves that go through your skin, hit the stone’s surface, and break it into smaller pieces that can pass more easily. You will likely receive anesthesia. Many patients go home the same day as their procedure and can resume their normal activities in two or three days. Afterward, you might see blood in your urine, and you could still have some discomfort while the remaining kidney stone fragments pass. We might prescribe medication to help them pass.

SWL isn’t recommended for people with large or hard stones.

If your kidney stone doesn't pass on its own, we might recommend shock wave lithotripsy as a non-invasive intervention. Accompanying issustration of kidney with stones and photo of shock wave lithotripsy machine.

Percutaneous nephrolithotomy (PNL)

Illustration of remove kidney stones

PNL can be helpful for people with larger kidney stones. You will be anesthetized for the procedure. A small incision will be made in your back or side. This incision allows doctors to examine your kidney with a tool called a nephroscope. Another instrument, which can break stones and remove them with suction, is passed through the nephroscope.

After the procedure, you might have a tube in your kidney (called a nephrostomy tube) for a day or two to allow urine to pass into a bag outside your body. You might also have a temporary stent.

In addition, we might order x-rays to make sure there are no residual kidney stones left. If any stones are found, they can be removed while you are still in the hospital.

Depending on the extent of your treatment, you might be in the hospital for a few days for PNL. You should be able to return to your usual activities in a week or two.

Which procedure is best?

As mentioned above, the answer depends on your situation. For example, shock wave lithotripsy has low complication rates, but ureteroscopy could address all the stones with one procedure.

Patients who don’t have success with the approaches mentioned above may need to have laparoscopic, open, or robot assisted surgery to remove the stone. These approaches are more invasive and not as common.

What are stents?

Your treatment might include a ureteral stent, especially if a stone is blocking one of your ureters. A stent is a plastic tube that keeps the ureter open so that urine can flow around the stone. A stent may also be used after surgical procedures so that the ureter can heal.

Some people need stents for just a couple of days. For others, the time frame might be longer. If your stent is uncomfortable, we can prescribe medication.

Kidney stones without symptoms

As we mentioned earlier, not all stones have symptoms. You might not even realize you have a stone until you have an imaging test for another health issue. In these circumstances, stones might not need treatment. However, we might recommend having asymptomatic stones removed if we think they will grow and cause discomfort later. You’ll need to think about how quickly you could get treatment if the stone started giving you trouble.

Preventing future kidney stones

Once you’ve had a kidney stone, you’re at higher risk for having another one.

Once you’ve had a kidney stone, you’re at higher risk for having another one. During your follow-up appointments, we’ll monitor your situation and conduct urine, blood, and imaging tests as needed. We’ll also analyze your original kidney stone(s) if we can. Knowing what they’re made of can help us develop a plan going forward.

There are also steps you can take to lower your risk for another stone. We’ll provide specific instructions tailored to your situation. But some of the most common prevention strategies include the following:

Close up of construction worker in hard hat drinking water

Drink more fluids

Your doctor will recommend the right amount of fluids for you, but experts generally recommend drinking about 10 servings of 10 fluid ounces each day. (Some experts say 3 quarts or 3 liters.) This will increase the amount of urine that your kidneys process and help substances dissolve so they won’t form crystals in the future.

Water is ideal, but other beverages, like tea and coffee, “count” toward your fluid intake. It’s not a bad idea to keep a checklist of the amount of fluid you’ve had each day. It also helps to use bottles and cans that list fluid measurements on the label.

Sugary drinks, like soda, should be avoided.

Change your diet

We’ll go over your diet with you thoroughly. You might need to eliminate or cut down on salty foods, like cheese, deli meats, and certain snacks. You might need to reduce your calcium intake or eat foods that are low in oxalate. Or, we might recommend eating less animal protein (meat, fish, poultry, etc.).

Take medications as directed. 

Depending on your situation, we might prescribe drugs like

  • thiazide diuretics – a type of drug that increases urine flow
  • Allopurinol – a drug that decreases uric acid production
  • potassium citrate – a drug that makes urine less acidic
  • acetohydroxamic acid – medication used to treat bladder infections, which can cause struvite stones
  • or cystine-binding thiol drugs- medications used to dissolve cystine stones

We will explain any medication’s purpose and be sure you understand how and when to take it.

Pay attention to your urologic health

If you notice anything unusual – pain with urination, for example – give us a call. We’ll be watching for urinary tract infections (UTIs) and other conditions that may affect your urologic health.

Resources

American Family Physician

“Preventing Kidney Stones with Diet and Nutrition”

(December 1, 2011)

https://www.aafp.org/afp/2011/1201/p1243.html

American Kidney Fund

“Kidney Stones; Causes, symptoms and treatment options”
(Last updated: May 14, 2024)
https://www.kidneyfund.org/all-about-kidneys/other-kidney-problems/kidney-stones

American Urological Association

“Medical Management of Kidney Stones (2019)”
(Published 2014. Reviewed and validity confirmed 2019)

https://www.auanet.org/guidelines/kidney-stones-medical-mangement-guideline#x2864

“Surgical Management of Stones: AUA/Endourology Society Guideline (2016)”

(Published 2016)

https://www.auanet.org/guidelines/kidney-stones-surgical-management-guideline

Healthline.com

Roland, James

“Hard Water vs. Soft Water: Which One Is Healthier?”

(July 30, 2019)

https://www.healthline.com/health/hard-water-and-soft-water

Watson, Stephanie

“Struvite: The Less Common Type of Kidney Stone”

(March 12, 2018)

https://www.healthline.com/health/kidney-health/struvite-stones

MedlinePlus.gov

“Allopurinol”

(Page last updated: August 15, 2017)

https://medlineplus.gov/druginfo/meds/a682673.html

“Parathyroid Disorders”

(Page last updated: October 21, 2020)

https://medlineplus.gov/parathyroiddisorders.html

“Uric acid – blood”

(Page last updated: October 8, 2020)

https://medlineplus.gov/ency/article/003476.htm

Medscape

Biyani, Chandra Shekhar, MS, MBBS, DUrol, FRCS(Urol), FEBU

“Cystinuria Treatment & Management”

(December 12, 2019)

https://emedicine.medscape.com/article/435678-treatment#d6

National Kidney Foundation

“How common are kidney stones?”

(Date reviewed: June 7, 2020)

https://www.kidney.org/atoz/content/kidneystones

“NKF Answers Top 10 Questions about Kidney Stones”

https://www.kidney.org/news/ekidney/november10/Top10_November10

“Distal Renal Tubular Acidosis (dRTA): What is dRTA and how is it diagnosed?”

(Reviewed: June 7, 2019)

https://www.kidney.org/atoz/content/distal-renal-tubular-acidosis-drta-what-drta-and-how-it-diagnosed

“What are Cystine Stones?”

(Last reviewed: March 8, 2016)

https://www.kidney.org/atoz/content/what-are-cystine-stones

UpToDate.com

Preminger, Glenn M., MD
“Kidney stones in adults: Surgical management of kidney and ureteral stones”
(Last updated: August 12, 2024)
https://www.uptodate.com/contents/kidney-stones-in-adults-surgical-management-of-kidney-and-ureteral-stones

Preminger, Glenn M., MD and Gary C. Curhan, MD, ScD

“Patient education: Kidney stones in adults (Beyond the Basics)”

(Last updated: May 16, 2023)

https://www.uptodate.com/contents/kidney-stones-in-adults-beyond-the-basics

Urology Care Foundation

“Did You Know? Ureteral Stents”

(Summer 2020)

https://urologyhealth.org/healthy-living/urologyhealth-extra/magazine-archives/summer-2020/did-you-know-ureteral-stents

“What are Kidney Stones?”

(Updated: April 2020)

https://www.urologyhealth.org/urologic-conditions/kidney-stones

WebMD

“Acetohydroxamic Acid Tablet”

https://www.webmd.com/drugs/2/drug-8724/acetohydroxamic-acid-oral/details


Low Testosterone/Testosterone Deficiency

Testosterone is the reason males develop characteristics like facial hair and a deeper voice. It drives a man’s libido and helps with erections. It’s also involved with sperm production, muscle strength, and bone health. Produced by the testicles, testosterone is what’s known as an androgen—a hormone responsible for masculine traits. (Note: While women’s bodies produce testosterone in smaller amounts, it is usually considered a male hormone.)

Sometimes, men don’t produce enough testosterone (this is called hypogonadism or “low testosterone”)

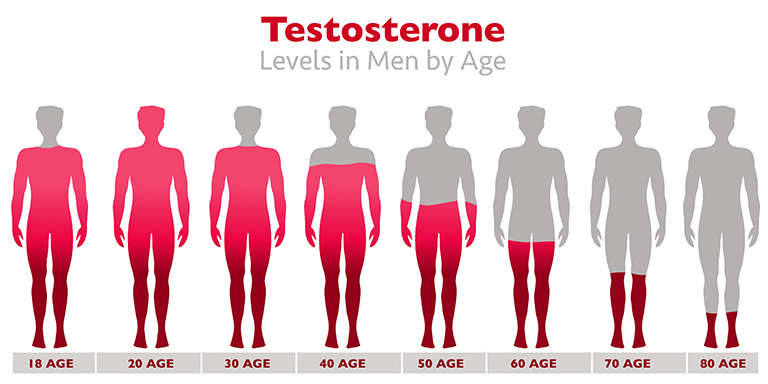
Sometimes, men don’t produce enough testosterone (this is called hypogonadism or “low testosterone”). This may happen due to a congenital condition (something a man is born with), an injury, cancer treatment, or other reasons. In addition, men’s testosterone levels decline as they get older.

When low testosterone is accompanied by other symptoms, like low sex drive, fatigue, and moodiness, urologists make a diagnosis of testosterone deficiency (TD).

The Urology Care Foundation estimates that 2% of men have TD. It is more frequent in older men, overweight men, and men with diabetes.

What are the symptoms of testosterone deficiency?

The typical symptoms of TD include the following:

Less interest in sex
Erectile dysfunction
Fatigue
Moodiness, depression, or irritability
Loss of muscle mass
Weaker bones
Less body or facial hair
Development of breasts (gynecomastia)

TD symptoms are similar to symptoms of other conditions. For example, trouble with erections can be a sign of diabetes or heart disease. Low sex drive could be linked to depression or be a side effect of medication. For these reasons, it’s a good idea to call your doctor if you have any of these symptoms so you can have a thorough medical exam.

What causes testosterone deficiency?

Congenital conditions

These are medical conditions that you’re born with. On example is Klinefelter syndrome, when a genetically male child is born with an extra X chromosome. Children with Klinefelter syndrome may have smaller testicles that produce less testosterone.

Children with intersex conditions (development of both male and female reproductive organs) may also have trouble with testosterone production.

Pituitary gland disorders

The pituitary gland is a tiny gland found in the brain. It produces, or stimulates the production of, many hormones. In men, it “tells” the testicles to make testosterone. If there is a problem with the pituitary gland, the testicles might not get the “message” to produce.

Trauma

Testicles that have been injured in an accident or through pelvic trauma may not function properly.

Cancer treatment

If a man has one or both testicles surgically removed, his body will produce less testosterone. Chemotherapy and radiation can affect testosterone production, too.

Obesity

Testosterone deficiency is more common in men who are overweight or obese. That’s because fat cells convert testosterone to estrogen, another type of hormone. In addition, obese men may have lower levels of sex hormone binding globulin (SHBG), a substance that carries testosterone through the bloodstream. Weight loss might help restore testosterone levels.

Age

When men reach their thirties, their bodies start producing less testosterone. The decline is gradual—about 1% each year—and might not be noticeable at all. Some people call this change andropause or male menopause, comparing the testosterone decline to the drops in estrogen production in women’s bodies during menopause. However, this comparison is not accurate. Men’s testosterone levels decline gradually, while women’s estrogen levels fall more quickly over time.

Here are some other issues that can contribute to TD:

  • Autoimmune disorders
  • Infections
  • Medications (such as antidepressants, opioids, and narcotics)
  • Liver disease
  • Kidney disease
  • Diabetes
  • Metabolic syndrome (high blood pressure, high blood sugar, unhealthy cholesterol levels, excess belly fat)
  • HIV and AIDS
Testosterone levels decline in men as they age

How is testosterone deficiency diagnosed?

When diagnosing TD, several factors are considered:

Blood tests

Several substances are checked during blood tests.

Total testosterone

Testosterone circulates in the bloodstream, and it is classified in two different ways. Attached testosterone attaches to proteins in the blood. Free testosterone circulates on its own, not attached to another substance. Most testosterone is attached.

For the purpose of diagnosing TD, doctors assess total testosterone (both attached and free), which is measured in nanograms per deciliter (ng/dL). For context, think of a typical paper clip, which weighs about a gram. A nanogram weighs one-billionth of a gram. A deciliter represents one-tenth of a liter. (To visualize a liter, think of a liter of soda.)

The American Urological Association (AUA) defines a “normal physiologic” testosterone range as 450-600 ng/dL.

For a TD diagnosis, the AUA uses a cutoff of 300 ng/dL. In other words, men whose total testosterone levels are below 300 ng/dL could be diagnosed with TD.

Doctors conduct two blood tests on different days. Both tests are done in the early morning because a man’s testosterone levels fluctuate throughout the day. Levels are usually higher in the morning and lower at night. The protocol of testing in the morning keeps measurements consistent.

Luteinizing hormone (LH)

Produced by the pituitary gland, luteinizing hormone spurs testosterone production by the testes. If LH levels are abnormal, there could be a problem with pituitary gland function or a hormone disorder.

Prolactin

Prolactin is another hormone produced by the pituitary gland. High levels might signal an issue with this gland.

Hemoglobin and hemocrit

Red blood cells contain hemoglobin, a substance that brings oxygen from the lungs to other parts of the body. Hemocrit refers to the percentage of red blood cells found in the blood. High levels of hemocrit could signal polycythemia – an increase in red blood cells that can lead to blood clots. Polycythemia can be a side effect of TD treatment, so it is helpful to get baseline values during diagnosis.

Medical history

Doctors will likely ask about the following:

  • Any symptoms associated with low testosterone
  • Prescribed medications and use of other drugs
  • Past illnesses
  • Past traumas, accidents, and surgeries
  • Illnesses that run in the family
  • Development at puberty

Other assessments

During a physical exam, providers usually check the following:

  • BMI (body mass index)
  • Waist circumference
  • Blood pressure
  • Cholesterol and triglyceride levels
  • Blood sugar
  • Hair patterns
  • Testicle size
  • Prostate size
  • Development of breasts (gynecomastia)

Other tests, if necessary.

Estradiol. If a man has shown some breast development, doctors may check his levels of estradiol, a form of estrogen.

PSA (prostate-specific antigen). Men over age 40 may have their PSA levels checked. High PSA could indicate a prostate condition, such as prostate cancer. Because testosterone replacement therapy, a typical treatment for TD, can be risky for men with prostate cancer, it’s important to screen for prostate cancer before any treatment begins.

How is testosterone deficiency treated?

When considering treatments for TD, we first consider the cause.

When considering treatments for TD, we first consider the cause. If we can pinpoint the reason a man’s testosterone levels are low, treating the underlying condition might be the first step toward improvement. For example, if a man has low testosterone due to obesity, we might suggest weight loss, a healthy diet, and exercise.

Testosterone replacement therapy (TRT) is another option. TRT has 2 goals: to boost testosterone levels into a normal range (usually between 450 and 600 ng/dL) and to relieve the symptoms a patient is experiencing due to his testosterone deficiency. Usually, improvement of symptoms occurs within the first 3 months of treatment.

Testosterone therapy can be administered in several ways.

Testosterone preparations are available by prescription; in fact, testosterone prescribed by a healthcare professional is the only safe way to treat TD. It can be administered in several ways, and we’ll talk with you about your personal situation, medication preferences, insurance coverage, and out-of-pocket costs:

Gels, creams, and patches

These are called transdermal or topical treatments: they are applied to the skin. For example, a man might apply a gel to his belly every day or a patch to his shoulder every few days. Specific instructions are provided. Often, the exact dose is pre-measured in a corresponding pump or tube.

Advantage:

  • Application is easy and convenient.

Disadvantages:

  • Some men develop rashes or itching from topical testosterone treatments.
  • Men need to be careful when using topical testosterone and make sure that the product does not transfer to anyone else, especially women or children.

Men are advised to cover the treatment area and keep products in a safe place, out of reach for children and pets.

Men should also wash their hands thoroughly after applying testosterone. Clothing that has come into contact with testosterone should be washed separately.

Why is avoiding testosterone transfer to others so important? Women who come into contact with topical testosterone may develop unusual hair growth or acne. In pregnant women, testosterone exposure may harm the unborn baby. Exposure in children may lead to enlarged genitals, pubic hair growth, increased sexual desire, increased erections, aggressive behavior, and bone growth issues.)

Injections

Some men go to their doctor’s office to receive testosterone injections. Others self-inject their prescribed medicine at home. Frequency can vary from one injection every week to one injection every 10 weeks. (Most men have an injection every 2 weeks.) Shots may be placed just under the skin or directly into a muscle.

Advantages:

  • Injectable testosterone tends to be the most affordable option.
  • The dosing schedule may be more convenient.

Disadvantages:

  • Testosterone levels can fluctuate. Typically, testosterone levels increase right after the injection, then gradually decrease until the next one. (In some cases, the dosing protocol might be changed to 1 injection once a week to even out the amount of testosterone given over time.)
  • Some men might be uncomfortable with the idea of injections.
  • Men may still need to travel to a doctor’s office to receive injections.
  • Allergic reactions are another potential side effect.

By mouth

This route is also called oral or buccal (buccal is a word that refers to the cheek or mouth cavity and in this case refers to placing a patch between the gum and cheek). Options might include capsules to swallow or patches to place on the gum.

Advantage:

  • Taking testosterone by mouth may be less invasive.

Disadvantages:

  • Some men experience gum irritation, pain, headache, or a bitter taste in the mouth. Gum disease (gingivitis) is possible as well.

Through the nose (intranasal)

Testosterone in gel form is pumped into the nostril.

Advantage:

  • The delivery method is less invasive. One form of intranasal testosterone, Natesto, may have fewer effects on fertility, but more research is needed. See more details below.

Disadvantages:

  • Men may need to take their medicine 3 times a day, which could be inconvenient.
  • Side effects may include congestion, nasal irritation, scabbing, a runny nose, or changes in smell.

Pellets

Administered by a doctor, pellets are placed under the skin and gradually dissolve. Treatment needs to be repeated every 3 to 6 months.

Advantage:

  • The dosing schedule can be convenient. Men do not need to remember to take medication every day or every week.

Disadvantages:

  • Testosterone pellets need to be administered at a doctor’s office.
  • Administration is more invasive.
  • After pellet implantation, some men experience pain, swelling, or bruising.

How often should a man on TRT see his doctor?

About 2 to 4 weeks after starting testosterone therapy, patients need to return for a checkup. At this time, lab results and symptoms are re-assessed. If results are satisfactory, further assessment is recommended every 6 to 12 months.

If necessary, estradiol and PSA levels will also be assessed periodically.

Hematocrit levels may also be monitored. Hematocrit is a measure of the percentage of red blood cells on the blood. As mentioned earlier, polycythemia— excess amounts of red blood cells—is a possible side effect of TRT. Polycythemia can thicken the blood and raise a person’s risk for stroke or blood clots.

If TRT raises testosterone levels but does not improve symptoms, providers may recommend that men stop TRT. It’s possible that the symptoms are not related to TD, and further evaluation could be necessary.

Is it okay to take over-the-counter TRT medications or order them online?

Men should always have TRT under the care of a qualified medical professional.

You might see testosterone supplements at pharmacies, department stores, or online. Are they safe to use?

No, they’re not. And here’s why:

  • Supplements are not regulated by the FDA (U.S. Food and Drug Administration). Therefore, the safety of these products cannot be guaranteed.
  • Supplements can contain ingredients that interact with other medications you take. This can make you sick.
  • Some supplements have ingredients that aren’t listed on the product label, so you might not know exactly what you are getting.

Urologists tailor treatment to a patient’s personal situation, prescribing formulations that are safe and effective for you. We will also monitor your health after you start testosterone therapy, making any adjustments as needed.

Special Concerns

How might testosterone replacement therapy affect a man’s fertility?

Men who wish to father children may wish to consult a reproductive health specialist before starting testosterone replacement therapy.

Testosterone preparations can reduce a man’s levels of follicle-stimulating hormone (FSH), which triggers sperm production. As a result, testosterone therapy could lower sperm count. Men who are hoping to become a father need to carefully consider the risks testosterone replacement therapy may present to fertility.

Depending on the cause of TD, there might be other medications a man can take to raise his testosterone levels. Some examples are aromatase inhibitors (AI), human chorionic gonadotropin (hCG), and selective estrogen receptor modulators (SERM). Sometimes, a combination of these medications is prescribed.

Note: In September 2020, scientists reported that a nasal testosterone preparation called Natesto may have a less negative impact on sperm production. However, more research is needed before this medication can be safely prescribed to men who wish to preserve fertility.

Is TRT linked to prostate cancer?

No, there is no evidence that connects testosterone therapy to prostate cancer. However, a man’s PSA levels might increase during testosterone therapy, so it is important to monitor them.

Is TRT linked to other health risks?

There have been concerns about testosterone therapy and cardiovascular events, like strokes, blood clots, and heart disease. However, it is not definitely known whether TRT raises or lowers risk of cardiovascular problems. Men are encouraged to discuss any heart concerns with their doctor.

The AUA recommends that men who have had a cardiovascular event wait 3 to 6 months before starting TRT.

It should also be noted that low testosterone itself can be a risk factor for cardiovascular disease.

Resources

American Urological Association

Mulhall, J.P., et al.
“Evaluation and Management of Testosterone Deficiency (2018)”
(Published: 2018)
https://www.auanet.org/guidelines/guidelines/testosterone-deficiency-guideline

Videos included with above guidelines:

  • What is Testosterone Deficiency: Definition and Diagnosis
  • Monitoring and Management the Testosterone Deficient Patient
  • Low Testosterone and Cardiovascular Risk
  • Fertility Preservation in the Testosterone Deficient Patient
  • Testosterone, PSA, and Prostate Cancer

Healthwise

“Nanograms per deciliter (ng/dL)”
(Current as of: June 17, 2021)
https://paleymd.com/patient-education/healthwise/?DOCHWID=stn166036

Hormone Health Network (The Endocrine Society)

“Low Testosterone (Hypogonadism)”
(Last updated: April 2020)
https://www.hormone.org/diseases-and-conditions/low-testosterone

“Pituitary Gland”
(Last updated: January 2019)
https://www.hormone.org/your-health-and-hormones/glands-and-hormones-a-to-z/glands/pituitary-gland

“Testosterone Treatments”
(Last updated: March 2018)
https://www.hormone.org/your-health-and-hormones/mens-health/testosterone-treatments

“What is Luteinizing Hormone?”
(Last updated: November 2018)
https://www.hormone.org/your-health-and-hormones/glands-and-hormones-a-to-z/hormones/luteinizing-hormone

The Journal for Nurse Practitioners

Luthy, Karlen E., DNP, FNP, et al.
“Comparison of Testosterone Replacement Therapy Medications in the Treatment of Hypogonadism”
(Full-text. Published: 2016)
https://www.npjournal.org/article/S1555-4155(16)30716-4/pdf

The Journal of Sexual Medicine

Lundy, Scott D., MD, PhD, et al.
“Obstructive Sleep Apnea Is Associated With Polycythemia in Hypogonadal Men on Testosterone Replacement Therapy”
(Full-text. Published: April 16, 2020)
https://www.jsm.jsexmed.org/article/S1743-6095(20)30169-7/fulltext

The Journal of Urology

Ramasamy, Ranjith, et al.
“Effect of Natesto on Reproductive Hormones, Semen Parameters and Hypogonadal Symptoms: A Single Center, Open Label, Single Arm Trial”
(Abstract. Published: September 1, 2020)
https://www.auajournals.org/doi/10.1097/JU.0000000000001078

Medical News Today

Johnson, Jon
“Polycythemia: Everything you need to know”
(December 16, 2019)
https://www.medicalnewstoday.com/articles/polycythemia

MedlinePlus.gov

“Hemoglobin Test”
(Page last reviewed: July 31, 2020)
https://medlineplus.gov/lab-tests/hemoglobin-test/

“Klinefelter Syndrome”
(Topic last reviewed: June 5, 2017)
https://medlineplus.gov/klinefeltersyndrome.html

“Prolactin Levels”
(Page last reviewed: December 17, 2020)
https://medlineplus.gov/lab-tests/prolactin-levels/

“Testosterone Levels Test”
(Page last reviewed: December 3, 2020)
https://medlineplus.gov/lab-tests/testosterone-levels-test/

“Testosterone Topical”
(Page last reviewed: December 6, 2021)
https://medlineplus.gov/druginfo/meds/a605020.html

ReproductiveFacts.org (American Society for Reproductive Medicine)

“Testosterone Use And Male Infertility”
(Created: 2015)
https://www.reproductivefacts.org/news-and-publications/patient-fact-sheets-and-booklets/documents/fact-sheets-and-info-booklets/testosterone-use-and-male-infertility/

UpToDate

“Patient education: Low testosterone in men (The Basics)”
(Topic retrieved on November 11, 2021)
https://www.uptodate.com/contents/low-testosterone-in-men-the-basics

Urology Care Foundation

“Testosterone Therapy – What You Should Know”
(2020)
https://www.urologyhealth.org/educational-materials/testosterone-therapy

“What is Low Testosterone?”
https://www.urologyhealth.org/urology-a-z/l/low-testosterone

WebMD

Hoffman, Matthew, MD
“Low Testosterone and Your Health”
(Reviewed: February 7, 2021)
https://www.webmd.com/men/what-low-testosterone-can-mean-your-health


Male Infertility

If you and your partner have been having unprotected sex for a year without conceiving, you might want to consider scheduling a consultation with us to explore the causes of your potential infertility and the medical options available to address them. (If your partner is age 35 or older, the time frame is six months.) Infertility affects about 15% of couples in our country.

Conception is a complex biological process. That can be hard to remember when other couples seem to conceive so easily. But successful conception depends on many factors including glands, hormones, sex cell development, and one’s overall health. A thorough fertility examination will explore all the relevant factors.

A woman and man read an at-home pregnancy test

Causes of Male Infertility

Sperm cells are essential for fertilization. During ejaculation, the average man releases about 100 million sperm. Shaped like tadpoles, sperm cells swim to their egg.

But in some cases, men’s bodies produce too little sperm (oligospermia) or no sperm at all (azoospermia). Sperm cells also need to be well formed, with a proper head and tail, to be healthy. And they need to swim well to reach an egg cell.

Many factors can affect your sperm production and quality:

  • Your overall lifestyle habits like diet, exercise, alcohol consumption, and drug use.
  • Medications like drugs for arthritis, cancer, high blood pressure, and depression
  • Cancer treatments like chemotherapy, surgery, and radiation
  • Illness and infections, such as diabetes, multiple sclerosis, diabetes, sexually transmitted infections, and sickle cell anemia.
  • Congenital conditions present at birth, such as Klinefelter syndrome or congenital adrenal hyperplasia (CAH)
  • Obstructions. Sometimes, a man’s body can make sperm, but the cells can’t reach their destination because the path is blocked. Obstructions can be caused by infections, surgery, or developmental defects. And if a man has had a vasectomy, of course the path will be blocked.
  • Retrograde ejaculation. In this case, sperm cells can leave the testes, but they go backward into a man’s bladder instead of forward out of the penis during ejaculation. The sperm cells pass with a man’s urine. On its own, retrograde ejaculation isn’t harmful, but it makes it challenging to father a child.
  • Varicoceles. These swollen veins in the scrotum interfere with blood flow and drainage. The scrotum needs to be cooler for good sperm production, but varicoceles make the environment too warm.
  • Genetic problems. Sperm cells might not contain the correct amount and types of genetic material necessary to fertilize an egg cell.
  • Immunologic infertility. In this rare situation, antibodies produced by a man’s own immune system attack sperm cells and interfere with their movement.

Testosterone Deficiency (Hypogonadism)

The hormone testosterone is an integral part of sperm production. If a man has low levels of testosterone, he might not produce enough viable sperm to create a pregnancy.

Hypogonadism can be caused by problems in testes (the glands that make sperm, also called testicles), such as from testicular injury or cancer treatment.

Problems in the hypothalamus and the pituitary gland – two areas of the brain that trigger testosterone production – can also lead to low testosterone levels.

Diagnosis

Your Medical History

At this stage, we will gather information about your overall health. It’s important to be candid and honest in your answers. Doing so gives us a clear picture of what factors may be contributing to your difficulties conceiving.

While taking your medical history, we will likely cover these topics:

  • Your health during childhood
  • Your experiences with puberty and sexual development
  • Your sexual history
  • Past illnesses or infections, including sexually-transmitted infections
  • Any surgeries you’ve had in the past
  • Any accidents or pelvic traumas you’ve experienced
  • Your lifestyle – drinking, smoking, use of recreational drugs or street drugs
  • Exposures to chemicals, like pesticides or heavy metals, that might impair fertility
  • Your family medical history

A Physical Exam

During a physical exam, we will assess your testicles (also called the testes), epididymis, vas deferens, and penis.

Your testes are the glands that produce sperm cells.

Testicles are connected to the epididymis. This coiled area is where sperm cells mature. They are also stored there until you ejaculate. Usually, there are enough sperm cells for two or three ejaculations. (Experts estimate that men aged 21 to 55 have can have up to 200 million sperm cells in each epididymis.) Sperm cells that are not ejaculated are absorbed by the body.

When a man is sexually stimulated, the sperm make their way to the vas deferens – a tube that connects the epididymis to the urethra in the penis. And from there, they are expelled out during orgasm. Sperm can be stored in the vas deferens, too.

We will also check your body fat, skin, hair, and breasts. Sometimes, a testicular or transrectal ultrasound is done to give another perspective. Together, these results may provide clues about testosterone deficiency or other conditions that can affect fertility.

Semen Analysis

You’ll probably have a semen analysis (sperm count), too. During this test, we look for several things:

  • How much semen you ejaculate (volume)
  • Semen characteristics (such as thickness, color, and acidity)
  • How many sperm cells your semen contains
  • Sperm cell morphology – the shape and structure of the cells and whether their heads and tails are well-formed
  • Sperm cell motility – the percentage of sperm that “swim” in a forward direction and how well they move, especially through cervical mucus
  • Total motile count (total number of moving sperm)

Typically, a semen analysis will be done in a specialized dedicated lab where you’ll be asked to masturbate in private, directing your ejaculate into a cup.

Producing a sample “on demand” can be a challenge for some men, so you might be able to do it at home in a sterile cup or condom we provide. Once you have your sample, it’s critical that you deliver it to the lab within an hour. Whenever possible, it is preferable to provide the specimen in the lab to avoid the transportation and delay challenges of home collection.

For best results, you should avoid ejaculating 3 days before giving your sample. You might have to give several semen samples over a period of weeks for us to provide a thorough analysis.

Blood tests

Sometimes, hormone levels interfere with a man’s fertility. Blood tests measure the levels of several hormones, such as the following:

  • Total testosterone
  • Follicle-stimulating hormone (FSH) – a hormone that triggers sperm production
  • Luteinizing hormone (LH) – a hormone that triggers testosterone production
  • Prolactin

Urinalysis

We might have you give a urine sample to check for health conditions that can affect fertility, like diabetes, kidney disease, and urinary tract infections (UTIs).

We might also check for the presence of sperm cells in your urine. This can happen if you have retrograde ejaculation.

Testicular Biopsy

If there is no sperm present in your semen, we might discuss performing a testicular biopsy combined with testicular sperm extraction (TESE). This procedure can reveal whether there are sperm cells in your testicular tissue. If there are, a section of your reproductive tract might be blocked, preventing sperm cells from leaving the testes (testicles). In other cases, there aren’t enough sperm cells to make it out to the ejaculate, but we can still find them in the testis in many instances.

If sperm cells are found, they will be removed during the extraction procedure, then safely preserved by the embryologist and stored for possible egg fertilization later. (An embryologist is a specialist who helps create and preserve embryos.)

Treatment Options

Your treatment for male infertility will depend on what’s causing it. Here are some examples:

  • Gonadtropin treatment. This hormonal approach is used when there are problems in the hypothalamus or pituitary gland – two areas of the brain that trigger testosterone production. Injections of gonadotropin (sometimes combined with follicle-stimulating hormone) are given about three times a week for six months or until sperm are produced.
  • Surgery. Some problems, like varicoceles and blockages, can be treated with surgery.
  • Medications (or medication adjustments) might be necessary as well.

Patience is key when you’re undergoing fertility treatment. Some approaches, such as gonadotropin treatment, can take up to two years.

Sperm Retrieval Methods

If you and your partner are having trouble conceiving through intercourse, you might consider assisted reproductive technologies (ART), such as in vitro fertilization (IVF). ART allows sperm cells to fertilize egg cells in a laboratory. We work with female reproductive endocrinologists and embryologists as a team to get the best results for couples.

For these paths, specialists can retrieve sperm in a few ways:

  • Testicular extraction. While a man is under local anesthesia, a needle is used to remove sperm cells directly from the testes.
  • Penile vibratory stimulation. A special vibrator is placed at the base of the penis to induce ejaculation for men who are unable to ejaculate on their own. Sperm cells are then retrieved from the semen. No anesthesia is required.
  • Rectal probe electroejaculation. This method triggers ejaculation with an electric probe (electroejaculator) placed into the rectum. Anesthesia is provided if necessary. Patients with certain types of spinal cord injury will need this procedure.

Coping With Infertility Testing and Treatment

Infertility testing, along with the uncertainty of whether you and your partner can conceive, is an emotional experience. Anxiety and depression are common for both men and women. Many people feel responsible or guilty, wondering whether it’s “their fault” there has been no pregnancy. Others feel especially sad when they see their peers having children or posting pictures of their families online.

Stress associated with infertility can actually make it more difficult to conceive. If you think this is an issue for you and your partner, know that you are not alone. It’s okay to seek emotional support. We can refer you to a mental health professional, such as a therapist or counselor, who works specifically with couples in your situation. You might also find a support group of peers – people who have been through what you’re going through now – to be beneficial.

These other tips may help, too:

  • Take care of your relationship. You and your partner are a team. Check in with each other and be open about how you’re feeling. Don’t bottle things up.
  • Try to still have fun. Make time to do things you enjoy together, whether it’s biking, traveling, watching movies, and yes – having sex, too. While you might feel pressured to have sex for baby-making, don’t forget that intimacy and pleasure are important, too.
  • Decide together how much you will tell other people about your fertility issues. Infertility is intensely personal. Depending on what you disclose, you might find friends and family offering advice you didn’t ask for or sharing stories that just don’t help. These people may be well-meaning, but sometimes their contributions cause more stress. There’s nothing wrong with keeping your private life private if that is what you need.
  • Take care of your overall health. Stick with healthy habits like good nutrition, proper exercise, and adequate sleep.

Resources

Johns Hopkins Medicine

“Overview of the Male Anatomy”
https://www.hopkinsmedicine.org/health/wellness-and-prevention/overview-of-the-male-anatomy

“Penile Vibratory Stimulation and Electroejaculation”
https://www.hopkinsmedicine.org/health/treatment-tests-and-therapies/penile-vibratory-stimulation-and-electroejaculation

UpToDate.com

Anawalt, Bradley D., MD and Stephanie T. Page, MD, PhD
“Patient education: Treatment of male infertility (Beyond the Basics)”
(Topic last updated: Jun 27, 2017)
https://www.uptodate.com/contents/treatment-of-male-infertility-beyond-the-basics

Kuohung, Wendy, MD and Mark D. Hornstein, MD
“Patient education: Evaluation of the infertile couple (Beyond the Basics)”
(Topic last updated: Jan 24, 2019)
https://www.uptodate.com/contents/evaluation-of-the-infertile-couple-beyond-the-basics

UrologyHealth.org (American Urological Association)

“What is Male Infertility?”
(No date provided)
https://www.urologyhealth.org/urologic-conditions/male-infertility

Verywellhealth.com

Boskey, Elizabeth, PhD
“The Anatomy of the Epididymis”
(Reviewed: September 1, 2020)
https://www.verywellhealth.com/epididymis-anatomy-4774615

Hayes, Kristin, RN
“The Anatomy of the Vas Deferens”
(Reviewed: July 9, 2020)
https://www.verywellhealth.com/vas-deferens-4846228

WebMD

“Sperm FAQ”
(Reviewed: October 30, 2018)
https://www.webmd.com/infertility-and-reproduction/guide/sperm-and-semen-faq#1


Nocturia and Bedwetting

Nocturia and bedwetting are two different, but related, situations. If a person has nocturia, they need to get up and urinate at least twice during the night. Bedwetting happens when a person urinates while asleep. They may not get the signal that their bladder is full, so they don’t wake up in time to use the bathroom.

Poor sleep associated with nocturia and bedwetting can make it difficult to function the next day. And if a sleep deficit continues, other health issues can develop.

Nocturia and bedwetting can take an emotional toll as well. You may feel embarrassed, ashamed, or reluctant to socialize, especially if you need to spend the night away from home.

However, nocturia and bedwetting are both quite common. They affect people of all ages, and they are nothing to feel ashamed of. They can also be managed, and talking to your doctor is an important first step.

Older woman with abdominal pain pushing herself up to a sitting position in bed

A note about bedwetting

In this article, we will focus mainly on adults. Bedwetting in childhood is not unusual, as it takes time for children to learn to fully control their bladder.

When bedwetting happens to adults, it is more likely to be a symptom of another health issue that needs treatment.

Poor sleep associated with nocturia and bedwetting can make it difficult to function the next day. And if a sleep deficit continues, other health issues can develop.

Who has nocturia?

Nocturia affects about 1 in 3 adults over age 30, according to the Urology Care Foundation. It becomes more common as people age.

Urologist describe nocturia in a couple of ways:

  • Nocturnal polyuria means your body produces too much urine overnight.
  • Global polyuria means the body is producing too much urine during the day and night.

What causes nocturia?

Sleep disorders, like insomnia and obstructive sleep apnea can also lead to nocturia.

Behavior patterns

Sometimes, nocturia is related to behavior. For example, your body might be “trained” to urinate at certain times during the night. Drinking too much fluid (especially alcohol and caffeinated beverages) in the hours before bedtime can make you wake up to urinate more often, too.

Medications, such as diuretics (water pills) may have nocturia as a side effect. If this is the case, your doctor might suggest changing the times you take your meds or adjusting your dose. (Always check with your doctor before making any changes.)

Sleep disorders, like insomnia and obstructive sleep apnea can also lead to nocturia.

Other health conditions

Nocturia is often associated with:

  • Pregnancy and childbirth
  • Pelvic organ prolapse (when a pelvic organ, such as the uterus or bladder, drops into a woman’s vagina)
  • Menopause
  • Urinary tract infections
  • Benign prostatic hyperplasia (an enlarged prostate)
  • Kidney stones
  • Limited bladder capacity, when your bladder cannot hold much urine
  • A history of bladder surgery
  • Swelling in the legs
  • High levels of calcium in the blood

In addition, nocturia can be a symptom of:

  • Diabetes
  • Heart disease and congestive heart failure
  • Vascular disease, which affects your blood vessels (veins and arteries)
  • Restless leg syndrome
  • Hypertension (high blood pressure)
  • Overactive bladder
  • Swelling in the legs

What is bedwetting?

Bedwetting happens when person doesn’t wake up in time to reach the toilet. Instead, they urinate while asleep, resulting in wet sheets and pajamas. The medical term for bedwetting is nocturnal enuresis.

Bedwetting is classified in two ways:

  • Primary bedwetting happens when a person wets the bed regularly for six months or more.
  • Secondary bedwetting happens when a person wets the bed after six months of not doing so.

In some cases, bedwetting is genetic. Adult bedwetting can run in families.

What causes bedwetting in adults?

In some cases, bedwetting is genetic. Adult bedwetting can run in families.

It can be a hormonal issue as well. Typically, the body creates a hormone called vasopressin, which allows the bloodstream to absorb water in urine, during the night. If the body doesn’t make enough vasopressin, this water may not be absorbed adequately, leading to bedwetting. (Vasopressin is sometimes called antidiuretic hormone or ADH.)

3d rendering of DNA molecules on the science background.

Problems with nerves can be another factor. Nerve signals between the brain and bladder should signal you to wake up to urinate. If they don’t, the bladder may release urine while you’re asleep.

Other health issues linked to adult bedwetting include:

Seeing your doctor for nocturia or bedwetting

If you’re experiencing persistent nocturia or bedwetting, make an appointment with your doctor. It can also help to keep a log with answers to these questions:

  • How often do you get up at night to urinate? How often do you wet the bed?
  • What fluids do you drink each day? How much do you have and when do you consume them? Do you have caffeine or alcohol?
  • Are you having any emotional distress?
  • Do you have any other symptoms, such as pain or changes in the amount of the urine you void?
Young man suffering from insomnia while lying in bed at night

Because nocturia and bedwetting can be a sign of underlying health problems, your doctor will likely order tests, which might include:

  • Urinalysis to check for chemicals and other substances in the urine
  • Urine culture to check for bacteria
  • Blood tests to check kidney function and blood sugar
  • Imaging tests to check your bladder
  • Cystoscopy to look inside your bladder and check for abnormalities

Often, treating the health problem helps relieve the nocturia or bedwetting.

Can I make lifestyle changes to manage nocturia and bedwetting?

Yes. You might try:

  • Limiting how much you drink at night, especially caffeine and alcohol. Skip that cup of coffee or nightcap after dinner.
  • Considering what time you take your medication. Ask your doctor about taking medications earlier so that you’ll be less likely to urinate during the night.

If you have nocturia, it may help to elevate your legs or wear compression stockings. This helps redistribute fluids so that they are absorbed by the bloodstream.

For bedwetting, there are products you can try:

  • Special alarms that are triggered by wetness. They will wake you up so you can finish urinating in the toilet. You could also set a regular alarm to empty your bladder at a set time.
  • Absorbent underwear
  • Waterproof mattress pads and sheet protectors

Are medications an option?

In some cases, your doctor might prescribe medication to help you with nocturia or bedwetting. Some examples include:

  • Desmopressin. This drug is a synthetic form of the hormone vasopressin and helps control water balance in your body.
  • Anticholinergic drugs. These drugs treat bladder spasms and overactive bladder. Some examples are oxybutynin and tolterodine.
  • Beta 3 agonists. These drugs, which include mirabegron and vibegron, relax bladder muscles and help increase the amount of urine the bladder can hold.

Other drugs prescribed for nocturia and bedwetting are imipramine, furosemide, and bumetanide.

What about surgery?

If less invasive strategies are not effective, surgery might be an option.

Some patients benefit from sacral nerve stimulation. The sacral nerves help with bladder control. This procedure involves implanting a special device that emits electrical signals to help your brain and bladder communicate with each other. It is a common treatment for overactive bladder.

Bladder augmentation is another strategy that increases the size of the bladder, allowing it to hold more urine.

Detrusor myectomy, another surgery type, removes some of the muscles around the bladder to better control the bladder contractions that release urine.

What else should I know about nocturia and bedwetting?

Remember that nocturia and bedwetting are common and nothing to be ashamed of! Be open with your doctor about your situation. They are there to help.

Resources

Cleveland Clinic

“Bedwetting”
(Last reviewed: January 20, 2023)
https://my.clevelandclinic.org/health/diseases/15075-bedwetting

“Augmentation Cystoplasty (Bladder Augmentation)”
(Last reviewed: September 7, 2023)
https://my.clevelandclinic.org/health/treatments/15846-augmentation-cystoplasty-bladder-augmentation

“Sacral Nerve Stimulation”
(Last reviewed: September 18, 2024)
https://my.clevelandclinic.org/health/procedures/sacral-nerve-stimulation

Mayo Clinic

“Adult bed-wetting: A concern?”
(January 31, 2023)
https://www.mayoclinic.org/diseases-conditions/urinary-incontinence/expert-answers/adult-bed-wetting/faq-20058456

“Mirabegron (oral route)”
(Portions of this document last updated: November 1, 2025)
https://www.mayoclinic.org/drugs-supplements/mirabegron-oral-route/description/drg-20075675

MedlinePlus

“Urinating more at night”
(Review date: July 1, 2023)
https://medlineplus.gov/ency/article/003141.htm

“Vibegron”
(Last revised: February 15, 2025)
https://medlineplus.gov/druginfo/meds/a621015.html

National Association for Continence

“Adult Bedwetting Causes and Treatments”
(Not dated)
https://nafc.org/adult-bedwetting

“What is Nocturia?”
(Not dated)
https://nafc.org/nocturia

Urology Care Foundation

“Nocturia”
(Updated: August 2023)
https://www.urologyhealth.org/urology-a-z/n/nocturia


Overactive Bladder

Most people are familiar with that occasional, urgent need to urinate—the feeling that there’s little time to spare and you need a bathroom ASAP.

But imagine having that feeling constantly. That’s the situation for people with overactive bladder (OAB). They may need to plan their day around bathroom availability, watching for the nearest restroom sign when they are away from home.

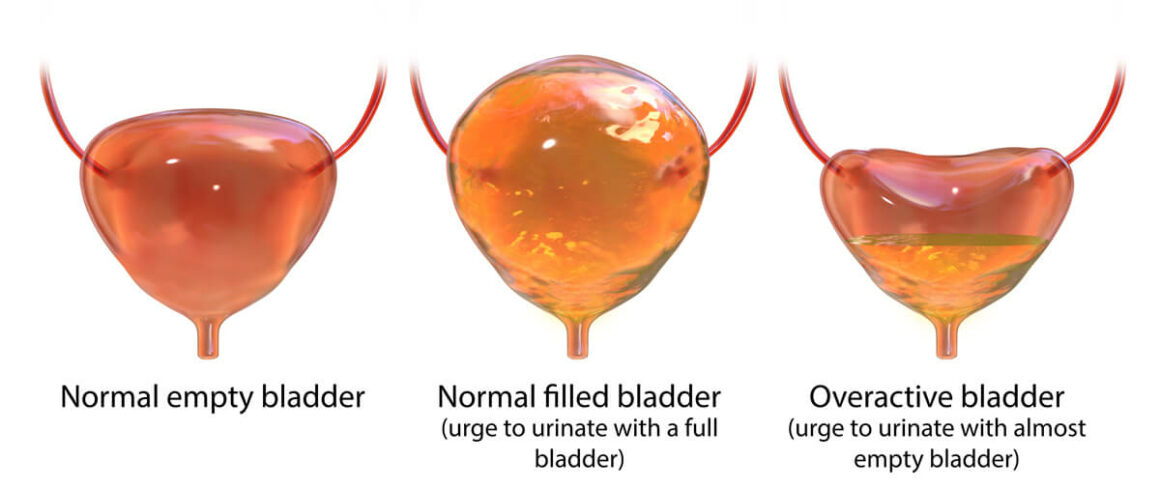
Overactive bladder is not a specific disease, but a group of symptoms:

  • An almost-constant, urgent need to urinate, even after the bladder has been emptied.
  • Urge incontinence. Some people with OAB leak urine, from a few drops to the entire contents of the bladder.
  • Waking up more than once during the night to urinate (nocturia).
  • Needing to urinate frequently, sometimes more than 8 times in 24 hours.
Illustration of: 1- normal empty bladder; 2- normal filled bladder (urge to urinate with a full bladder); 3- overactive bladder (urge to urinate with almost empty bladder)

OAB is sometimes called “spastic bladder” or “irritable bladder.”

OAB can affect a person’s emotional health, too. Many people feel anxious about urine leak accidents or embarrassed about needing the bathroom so frequently. They may shy away from socializing, feel isolated, and become depressed.

About 33 million people in the United States have OAB, according to the National Association for Continence (NAFC). It’s particularly common in older people, women who have gone through menopause, and men with prostate issues. People with neurological conditions like stroke or multiple sclerosis are also more likely to have OAB.

OAB is sometimes called “spastic bladder” or “irritable bladder.”

Some people think that poor bladder control is just something they have to live with, especially as they get older. But that’s not the case at all.

The good news is that OAB is treatable. With time and patience, OAB symptoms can greatly improve.

How does the urinary system work?

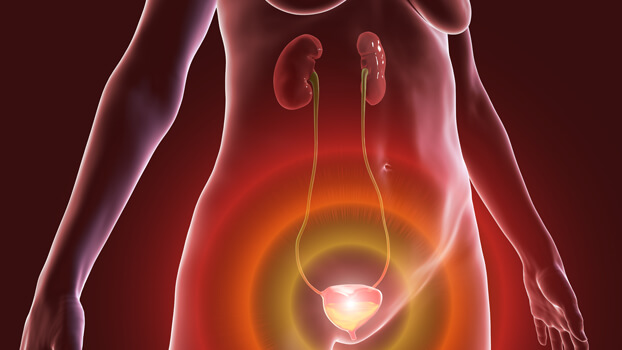
Typically, a person has two kidneys. These are the organs that make urine. Extending from each kidney is a ureter—a tube that connects to the bladder. Once produced, urine flows from the kidneys, through the ureters, to the bladder, where it is stored until a person urinates. On average, the bladder can hold about 2 cups (16 ounces) of urine before it needs to be emptied.

Illustration of kidneys connected to the bladder

At that time, the nerves in the bladder send a message to the brain, signaling the need for emptying. When it’s time to urinate, the brain sends a message to open the bladder’s sphincter muscle, which acts as a valve. Once open, urine flows from the bladder out of the body through a tube called the urethra.

With OAB, communication between the brain and bladder muscles are disrupted.

What causes overactive bladder?

With OAB, communication between the brain and bladder muscles are disrupted. As a result, a person will have that “I need go right now” feeling more urgently and more often. It also happens when the bladder isn’t full.

How is overactive bladder diagnosed?

Lots of people are reluctant to discuss urinary symptoms with a healthcare provider because it can be awkward and embarrassing to talk about bathroom issues. Hiding the problem doesn’t help and leads to unnecessary suffering.

When a person talks about urinary symptoms like those related to OAB with a healthcare provider, the provider will ask about the patient’s overall health and the medications currently being taken. They’ll also want to know about any past illnesses or surgeries.

They’ll also want more specific information about the urinary symptoms. For this reason, patients might be asked to keep a bladder diary for a few days.

A bladder diary is a place to jot down symptoms and urination patterns. It can be as simple as a spiral notebook or handwritten chart. Or it can be high-tech, like a smartphone app. Whichever method is chosen, these questions can reveal patterns:

  • How often is a patient urinating? What time of day?
  • What is the patient doing when he/she feels the need to urinate?
  • How strong is the urge to urinate?
  • How much urine is being released?
  • Are there any accidental urine leaks?
  • What is the patient eating and drinking? How much?
  • How do the circumstances affect the patient’s daily routine?

Urologists usually ask patients to keep a bladder diary for at least 3 days. Those days don’t have to be consecutive, but they should be 3 typical days. Patients should try to keep track of symptoms for 24 hours at a time.

In addition to the diary, doctors might ask patients to measure how much urine is released. A person might be given a special cup to use, or might use a cup from home, as long as it is known how much liquid it can hold.

When diagnosing OAB, urologists may conduct other assessments, too:

  • Physical exams. The doctor might feel your abdominal organs or conduct a pelvic or rectal exam.
  • Urinalysis. Lab technicians examine a urine sample under a microscope and check it for certain chemicals and substances.
  • Urine culture. Specialists use a urine sample to grow bacteria in a lab. You might have a urine culture if your doctor suspects a urinary tract infection or bladder infection in addition to OAB.
  • Post-void residual assessment. Using a catheter or ultrasound, the doctor checks to see how much urine remains in your bladder after you urinate. This test can provide clues about a bladder infection or blockage, which might share symptoms with OAB.

How is overactive bladder treated?

OAB can be treated in several ways. It may just be a matter of changing foods you eat and training your bladder to hold urine longer. Some people take medications to relax the bladder muscle. Others undergo certain procedures or, in rare cases, surgery. Sometimes, a combination of treatments is needed.

Lifestyle Changes

Patients might be able to adjust their daily habits to make them more bladder-friendly.

Dietary Changes

Certain foods and drinks can irritate the bladder:

  • Caffeinated and alcoholic beverages. These are called diuretics, and they cause the kidneys to make more urine.
  • Citrus fruits, like grapefruits, oranges, and lemons.
  • Sugar and artificial sweeteners.
  • Tomatoes and tomato-based foods like pasta sauce and ketchup.
  • Carbonated beverages, such as soda and seltzer water.
  • Spicy foods.
  • Onions.
  • Cranberries.
  • Chocolate.
  • Processed foods.

It can be hard to tell whether a specific food is triggering OAB symptoms. For this reason, an elimination diet can be helpful. With this diet, you stop consuming foods and drinks that could be triggers. Then, you gradually add them back, one by one.

For example, you might add oranges back to your diet. If your OAB symptoms worsen, then oranges are probably a trigger for you. But if you have no problems, then you can probably eat oranges with no problem.

Remember, everyone is different. A food that is an OAB trigger for one person may not trigger symptoms in another.

Some patients find that adding fiber to their diet improves OAB symptoms. Fiber may relieve constipation, which puts pressure on your bladder. Fiber is found in foods like whole grains, fruits and vegetables, and beans. An over-the-counter stool softener or laxative might be helpful, too.

Fluid Management

Your doctor can help you determine how much fluid to drink each day.

Double Voiding

Voiding is another term for urinating. Double voiding means urinating twice during the same bathroom visit. Urinate as you normally would, then wait a few seconds. Then try urinating again to empty your bladder.

Delayed Voiding

When you feel the urge to urinate, try waiting a few minutes before going to the bathroom. Over time, try increasing the waiting period. You might start with two or three minutes and gradually build up to waiting 2 or 3 hours. This process trains your bladder to wait longer between bathroom visits.

Timed Urination

This means training your bladder to urinate on a specific schedule. You might start by urinating when you wake up at 7 a.m. Then, plan bathroom visits every 2 to 4 hours, depending on what works for you.

Pelvic Floor Exercises

The pelvic floor muscle group supports your pelvic organs, including your bladder. Strengthening these muscles may improve OAB symptoms. Your doctor can teach you how to target these muscles and develop an effective exercise plan. (Kegel exercises are one example. Another is “quick flicks,” which involve quickly squeezing and releasing your pelvic floor muscles repeatedly.)

Pelvic floor physical therapy might include biofeedback. This technique uses electrodes placed on the abdomen or anal area to help patients identify and control their pelvic floor muscles.

Medications

If symptoms don’t improve with lifestyle changes, medication is usually the next step. We might recommend meds on their own or in combination with lifestyle changes. Sometimes, more than one medication is prescribed.

The most commonly used drugs for OAB are anti-muscarinics and β-adrenoceptor agonists, which can be taken by mouth or administered as a patch that you wear on your skin. These drugs relax the bladder muscle and allow the bladder to hold more urine.

These medications can have side effects, such as dry mouth, dry eyes, constipation, and blurred vision. If you experience these or any other side effects, let your healthcare provider know. Changing the dose or the type of medication might help.

Botox® Injections

If lifestyle changes and medications aren’t successful, injections of Botox® may be another option for treating OAB. Botox® can relax the detrusor muscle (found in the bladder wall) and relieve the urgent feeling. It can also help your bladder hold more urine.

Botox® therapy is given in a urologist’s office and takes about 20 minutes. After you’re given local anesthesia, the doctor inserts a hollow tube called a cystoscope through your urethra and into your bladder. The cystoscope has a camera at the end and allows the doctor to see the inside of your bladder. Botox® injections are given with a thin needle through the cystoscope.

After treatment, you might notice some blood in your urine or a burning sensation when you urinate. These side effects eventually go away. If necessary, medication can be prescribed to relieve some of the discomfort.

It may take a few days—or up to 2 weeks—to notice improvements in OAB symptoms. However, Botox® provides OAB relief for about 6 months, on average. For some people, relief lasts for up to a year. Still, the effect does diminish eventually, and repeat treatments are usually necessary.

Urinary retention—an inability to empty your bladder—can be a side effect of Botox® treatment. If this occurs, you might need to self-catheterize. This process involves inserting a flexible tube called a catheter through your urethra and into your bladder. Urine then drains from the bladder to the toilet or a collection bag. Your healthcare provider will show you how to use a catheter properly.

About 10% of patients experience allergic reactions to Botox®, which can include weakness, changes in vision, and breathing difficulties. Call your provider if these side effects occur.

Nerve Stimulation (Neuromodulation Therapy)

As noted above, OAB occurs when nerve signals between the bladder and brain don’t connect properly. Nerve stimulation uses electrical pulses to improve communication between these organs.

Nerve stimulation can be done in 2 ways:

Percutaneous tibial nerve stimulation (PTNS)

The word percutaneous means “through the skin” and tibial refers to the tibial nerve, located in the leg. With PTNS, electrical pulses are sent to your tibial nerve though an electrode placed under your skin, near your ankle. These pulses help nerve signals travel properly.

PTNS is typically administered in 12 weekly sessions, but some people need more sessions. Each session lasts for about 30 minutes. Side effects are rare, but some people experience mild pain, tingling sensations, bruises, or bleeding.

Sacral neuromodulation (SNS)

SNS involves the sacral nerve, which transmits messages among the brain, spinal cord, and bladder. This procedure is considered surgery and is completed in 2 parts.

The first step is a testing phase. After you’ve been given anesthesia, the surgeon places a small electrical wire beneath the skin in your lower back. This wire is connected to a special device called a stimulator, which triggers the electrical pulses. (Sometimes it is called a pacemaker.) This device runs on batteries and may be worn outside the body, but you can also hold it in your hand. For a few weeks, you and your doctor will test the process and see how it affects your OAB symptoms.

If the test is successful, you’ll have a second procedure to place a permanent stimulator device near the sacral nerve. You will still have a programmer to adjust the stimulation. You will also have follow-up appointments to make sure everything is running smoothly.

Possible complications of SNS surgery include pain, infection, bleeding, and wire movement. Let your doctor know if you have any discomfort.

The implanted, permanent device has a battery, which might need replacing (via surgery) in a few years.

Other Surgical Approaches: Bladder Reconstruction and Urinary Diversion

Severe cases of OAB may require bladder reconstruction or urinary diversion. However, these situations are rare.

  • Augmentation cystoplasty is surgery that makes the bladder larger, creating more space to store urine.
  • Urinary diversion creates a new path for urine to exit the body, bypassing the bladder.

Resources

American Urological Association

Lightner D.J., et al.
“Diagnosis and Treatment of Non-Neurogenic Overactive Bladder (OAB) in Adults: an AUA/SUFU Guideline (2019)”
(Guideline published: 2012; Amended in 2014 and 2019)
https://www.auanet.org/guidelines/guidelines/overactive-bladder-(oab)-guideline#x2904

Healthline.com

Ellis, Mary Ellen
“What Are the Best Medications for an Overactive Bladder?”
(Updated: September 2, 2018)
https://www.healthline.com/health/overactive-bladder/medications-for-overactive-bladder

Healthline Editorial Team
“Botox for Overactive Bladder”
(Updated: November 29, 2017)
https://www.healthline.com/health/overactive-bladder-botox

Wallace, Ryan
“11 Foods to Avoid if You Have OAB”
(September 28, 2017)
https://www.healthline.com/health/11-foods-to-avoid-if-you-have-oab

LiveScience.com

“How Much Urine Can a Healthy Bladder Hold?”
(December 4, 2012)
https://www.livescience.com/32330-how-much-urine-can-a-healthy-bladder-hold.html

MedlinePlus.gov

“Self catheterization – female”(Last reviewed: January 10, 2021)
https://medlineplus.gov/ency/patientinstructions/000144.htm

“Self catheterization – male”
(Last reviewed: January 10, 2021)
https://medlineplus.gov/ency/patientinstructions/000143.htm

“Urine culture”
(Last reviewed: October 10, 2020)
https://medlineplus.gov/ency/article/003751.htm

Medscape

Ellsworth, Pamela I., MD
“Overactive Bladder Treatment & Management”
(Updated: January 21, 2021)
https://emedicine.medscape.com/article/459340-treatment#d11

Rao, Pravin K., MD
“Augmentation Cystoplasty”
(Updated: March 2, 2021)
https://emedicine.medscape.com/article/443916-overview

Merck Manual – Consumer Version

Chung, Paul H., MD
“Urinalysis and Urine Culture”
(Content last modified: May 2020)
https://www.merckmanuals.com/home/kidney-and-urinary-tract-disorders/diagnosis-of-kidney-and-urinary-tract-disorders/urinalysis-and-urine-culture

National Association for Continence

“Ask The Expert: Can Kegels Really Help My OAB Symptoms?”
https://www.nafc.org/bhealth-blog/ask-the-expert-can-pelvic-floor-exercises-really-help-my-oab-symptoms

“Overactive Bladder”
https://www.nafc.org/overactive-bladder

National Institute of Diabetes and Digestive and Kidney Diseases

“Definition & Facts of Urinary Retention”
(Last reviewed: December 2019)
https://www.niddk.nih.gov/health-information/urologic-diseases/urinary-retention/definition-facts

“Urinary diversion”
(Last reviewed: June 2020)
https://www.niddk.nih.gov/health-information/urologic-diseases/urinary-diversion

Urology Care Foundation

“It’s About Time . . . And It’s About You: It’s Time to Talk About Overactive Bladder”
(2021)
https://www.urologyhealth.org/educational-resources/overactive-bladder

“What is Urinary Diversion?”
https://www.urologyhealth.org/urology-a-z/u/urinary-diversion

VoicesForPFD.org (American Urogynecologic Society)

“Botox® Injections to Improve Bladder Control”
(2018)
https://www.voicesforpfd.org/assets/2/6/Botox.pdf

WebMD

Brown, Steven
“What Is a Post-Void Residual Urine Test?”
(Medically reviewed: February 10, 2020)
https://www.webmd.com/urinary-incontinence-oab/post-void-residual-test

Watson, Stephanie
“What Is Electrical Stimulation for Overactive Bladder?”
(Medically reviewed: February 11, 2020)
https://www.webmd.com/urinary-incontinence-oab/overactive-bladder-electrical-stimulation


Penile Cancer: What Every Man Should Know

When it comes to men’s health, penile cancer might not be the first thing that comes to mind. But even though it’s pretty rare, especially in the United States and Europe where it accounts for less than 1% of all cancers in men, it’s still something all men should be aware of. Getting diagnosed with any kind of cancer is scary, but the good news is that penile cancer is treatable, especially if it’s caught early.

Understanding Penile Cancer

The Cellular Origins of Penile Cancer

So what exactly is penile cancer? It’s when healthy cells in the penis start growing out of control and form a tumor. Penile cancer most commonly begins in the skin cells of the penis, with the majority of cases (about 95%) being squamous cell carcinomas. These cancers originate in the flat, thin squamous cells that line the surface of the penis. Other less common types of penile cancer can start at a deeper point in the skin (basal cell carcinoma), from connective tissue, smooth muscle and/or blood vessels (sarcoma), from the glands (adenocarcinoma), or even melanocytes, the cells responsible for the skin’s pigment (melanoma). Identifying the origin of a patient’s cancer helps doctors determine the most effective treatment approach.

Prevalence of Penile Cancer in the United States and Worldwide

Now one might wonder – how common is this? Well, in the U.S., only about 1 in 100,000 men get penile cancer each year. However, the global incidence of penile cancer varies substantially, with higher rates observed in parts of Asia, Africa, and South America. These geographical variations can be attributed to differences in risk factors such as HPV (Human Papillomavirus) infection rates and smoking prevalence, among other factors. Despite these variations, the overall global prevalence remains low.

Penile Cancer Causes and Risk Factors

One of the most notable risk factors for penile cancer is infection with the Human Papillomavirus (HPV).

In the realm of men’s health concerns, penile cancer stands out due to its potential impact on health and quality of life. Scientists don’t know why healthy cells become cancer cells and form tumors. They have, however, identified factors that appear to increase a person’s risk:

HPV Infection and Penile Cancer: A Significant Link

One of the most notable risk factors for penile cancer is infection with the Human Papillomavirus (HPV). High-risk strains of HPV, particularly HPV 16 and 18, are known to cause several types of cancers, including penile cancer. The virus can increase the risk of penile cells becoming cancerous by altering their DNA.

Vaccination against HPV emerges as a powerful preventive measure, significantly reducing the risk of penile cancer associated with the virus. Early vaccination is recommended and can provide a safeguard against the development of all HPV-related cancers.

Uncircumcised Men and Increased Penile Cancer Risk

Not being circumcised might increase a man’s chances of getting penile cancer. Circumcision is a procedure that removes all or part of the foreskin, and it’s usually done when a boy is just a baby. Some experts think that getting circumcised as an infant can help prevent penile cancer later in life.

Researchers aren’t completely sure why circumcised men have a lower risk of penile cancer, but it might have something to do with other risk factors. For example, men who are circumcised can’t get a condition called phimosis, and they also don’t build up a substance called smegma under their foreskin (see more below).

Phimosis, Poor Hygiene, and Their Associations

Phimosis is when the foreskin of the penis cannot be fully retracted, which can create an environment that leads to penile cancer if hygiene is poor. These conditions can lead to the accumulation of smegma. This substance can irritate and inflame the penile tissues, increasing cancer risk. Addressing phimosis through medical treatment and maintaining good genital hygiene can help reduce this risk.

The Role of Tobacco Use in Increasing Risk

Smoking or other tobacco use is another well-established risk factor for penile cancer. Research shows that smokers are three to four and a half times more likely to develop this cancer compared to non-smokers. This link remains strong even when accounting for other factors like sexual history. All tobacco products (such as cigarettes, snuff, or chewing tobacco) contribute to a higher risk of developing the disease due to the harmful substances in tobacco that can damage the DNA of cells in the penis. Stopping tobacco use can decrease this risk, so men looking to improve their overall health and reduce their cancer risk might benefit from a tobacco cessation program.

Age

Penile cancer is more common in men over 50 years of age. However, penile cancer can affect men at any age.

PUVA treatment for psoriasis

Psoralen and ultraviolet A photochemotherapy (PUVA) is a type of radiation treatment for psoriasis. Researchers have found that men who undergo this treatment are at higher risk for penile cancer.

Lichen sclerosus

Lichen sclerosus is a skin condition that affects the genitals. It can raise a man’s risk for both HPV infection and penile cancer.

HIV and AIDS

Men with AIDS have a weakened immune system, which can raise their risk for both HPV infection and penile cancer.

Penile Cancer Signs & Symptoms

So what should a man look out for? The early detection of penile cancer can significantly influence outcomes and prognosis. Awareness of these warning signs can lead to early medical intervention.

Some of the more common symptoms include the following:

Alterations in Penile Skin

Initial signs often manifest as noticeable changes in the skin covering the penis, particularly on the glans, foreskin (for those who are uncircumcised), or even the shaft. These alterations might include:

  • Thicker areas of skin
  • Discoloration or new color variations
  • The emergence of lumps or sores, which may or may not bleed
  • The appearance of a reddish, velvety rash, particularly under the foreskin
  • The development of small, crusty bumps or flat, bluish-brown patches
  • Unusual discharge or bleeding, emitting a foul odor from under the foreskin

Sores or lumps associated with penile cancer are not always painful. However, any new growth or change that persists or worsens over a period of about four weeks warrants medical attention.

Swelling

Another sign can be swelling at the penis’s end, particularly when it causes difficulty or inability to retract the foreskin. This symptom requires prompt evaluation by a healthcare professional.

Lymph Node Changes

Penile cancer can spread to lymph nodes in the groin area, leading to swelling. While swollen lymph nodes can result from various causes, including infections, their enlargement due to penile cancer would feel like smooth lumps under the skin.

The Importance of Paying Attention to Symptoms

If a man notices any of these symptoms, he shouldn’t feel embarrassed – he should go see a doctor right away. Doctors have seen it all before and are there to help. The sooner penile cancer is found, the easier it is to treat. And it’s important to keep in mind, these signs don’t always mean it’s cancer. They can also be caused by other conditions, like infections. But it’s always better to get checked out just in case.

Diagnosing Penile Cancer

Understanding the process of diagnosing penile cancer can help demystify the various steps involved.

Step 1: Initial Consultation and Physical Exam

The steps involved in diagnosis often begin with a consultation and a comprehensive physical examination. During this initial visit, your healthcare provider will discuss your medical history and any symptoms you’ve been experiencing and conduct a thorough physical exam. Particular attention is paid to the penis, where the doctor will look for any signs of abnormal growths, lumps, or changes in the skin’s appearance. This non-invasive examination identifies potential concerns that warrant further investigation.

Step 2: Biopsy – The Cornerstone of Diagnosis

The next step is a biopsy if any suspicious areas are found during the physical exam. A biopsy involves removing a small sample of tissue from the affected area, which is then examined under a microscope by a pathologist. Biopsy is the most reliable method for diagnosing penile cancer, as it allows direct observation of cancer cells. Doctors may use several types of biopsies depending on the size and appearance of the lesion. Incisional biopsies remove part of the affected area and are often used for larger or ulcerated lesions. Excisional biopsies, where the entire lesion is removed, are typically done for smaller nodules or plaques. Lymph node biopsies might also be performed to check for cancer spread, using fine needle aspiration or surgical removal for deeper nodes or when the cancer has possibly spread to lymph nodes. For all the above procedures, healthcare providers administer either local anesthesia or general anesthesia – depending on the biopsy type–to minimize discomfort.

Step 3: Imaging Tests – Understanding the Extent

After a biopsy confirms penile cancer, imaging tests like C.T. (Computed Tomography) scans, MRI (Magnetic Resonance Imaging), and ultrasound might be used; these tests help determine the cancer’s extent, showing how far it has spread within the penis, to lymph nodes, or to other parts of the body. C.T. scans provide detailed cross-sectional images, MRIs offer detailed images of soft tissues, and ultrasounds use sound waves to visualize internal structures. Each imaging test has a specific role in staging the cancer and planning treatment.

Step 4: Pathology Reports and Further Evaluation

Following the biopsy and imaging tests, a pathology report will detail the type of cancer, its aggressiveness (grade), and its extent (stage). This report will guide the treatment plan. In some cases, additional tests or consultations with other medical specialists might be recommended to ensure a comprehensive approach to care. The findings in the pathology report enable healthcare professionals to recommend the most effective treatment options tailored to the individual’s specific condition.

Staging and Prognosis of Penile Cancer

Staging is a process that occurs after a diagnosis of penile cancer has been confirmed. It involves determining the extent of the cancer, including its size, depth of invasion, and whether it has spread to nearby lymph nodes or distant parts of the body. The staging process is important for determining the treatment plan, as it allows clinicians to customize the approach to the patient’s specific needs.
Penile cancer is typically staged using the TNM system, which considers:

T (Tumor): The size and depth of the primary tumor.
N (Nodes): Whether the cancer has spread to nearby lymph nodes.
M (Metastasis): Whether the cancer has spread to other parts of the body.

Based on the TNM classifications, penile cancer is then assigned a stage, from 0 (the least advanced) to IV (the most advanced). Lower-stage cancers are generally confined to the penis. In contrast, higher-stage cancers may have spread to lymph nodes or distant organs.

Prognosis of Penile Cancer

The prognosis of penile cancer depends on several factors, including the cancer’s stage at diagnosis, the type of cells involved, and the patient’s overall health. One of the most encouraging aspects of penile cancer treatment is the high success rate in early-stage diagnoses. When detected and treated early, the chances of a complete recovery and minimal impact on quality of life are significantly increased.
Factors that can affect the prognosis of penile cancer include:

Early Detection

Early-stage cancers (I and II) have a higher success rate of treatment, often with options that preserve the function and appearance of the penis.

Lymph Node Involvement

Cancer in the lymph nodes can affect the treatment choice and prognosis. Early lymph node detection and treatment are key to improving outcomes.

Type of Cancer Cells

Certain types of penile cancer may be more aggressive and require more intensive treatment.

Penile Cancer Treatment Options

Treatment options for penile cancer largely depend on the extent of the cancer and how far it has spread. Some men undergo a combination of treatments. Therapies may destroy cancer cells, stop their growth, or both.

Surgical Options: Tailored Approaches for Best Outcomes

Surgery is often the primary treatment for penile cancer, and the specific surgical procedure selected depends on the cancer’s stage and location. The goal is always to remove the cancer while preserving as much normal function and appearance as possible.

Limited Excision (including circumcision): Cancer cells are cut out directly. Surrounding skin may also be removed. If the wound is small, it may be closed with stitches. More extensive wounds may be closed with a skin graft.

Mohs Micrographic Surgery: A precise technique where cancerous tissue is removed layer by layer, examining each layer under a microscope until no cancer cells are detected. It’s beneficial for small, early-stage tumors and aims to preserve penile tissue.

Laser Ablation: This treatment utilizes a high-intensity light to destroy cancer cells. It is suitable for small surface tumors and offers the benefit of minimal tissue damage.

Total glans resurfacing: TGS involves the removal of the skin and lamina propria layers of the glans penis (the tip of the penis), reaching down to the corpus spongiosum, and is followed by the application of a skin graft.

Glansectomy: If the cancer cells are confined to the glans, they might be surgically removed. Surgeons may be able to build a new glans with skin grafts.

Partial Penectomy: This surgery involves removing part of the penis, but enough of the penis is preserved to allow the patient to urinate standing up. It’s considered for larger tumors.

Total Penectomy: The removal of the entire penis, used for very large tumors or when the cancer is in the body of the penis. Urination is still possible through a new opening created in the perineum.

It might be possible to reconstruct the penis in a procedure called phalloplasty. Surgeons use tissue from other parts of the body and might add a penile implant to allow for erections. These surgeries are done after the penectomy once it is certain that the cancer cells are gone.

In cases where the cancer is very advanced, sometimes the scrotum and testicles are removed as well. Without the testicles, the man’s body will no longer produce adequate amounts of the hormone testosterone. However, hormone replacement therapy may be an option.

Lymph node surgery: Treating penile cancer that has spread to the lymph nodes near the groin and pelvis follows an established, step-by-step protocol. Penile cancer usually spreads from one area to another in a known pattern before it reaches more distant parts of the body. How much the cancer has spread to the lymph nodes greatly affects a person’s prognosis. Doctors use different tests like ultrasounds and biopsies to examine the nodes. They then decide on the best treatment by looking at things like the primary tumor stage and tumor grade and if it has spread to the lymph channels or nerves. Men with a higher risk of their cancer spreading get more intense treatments focused on the lymph nodes. Newer surgery methods that are less harsh are now also used, especially for those whose cancer hasn’t spread as extensively. What the tests show about the cancer will decide if the person needs to be watched closely or needs more treatment, like surgery or other therapies.

Non-surgical treatments

Non-surgical treatments for penile cancer may include:

Topical therapy: Topical means that medicine is applied directly to the skin of the penis.

One type is topical chemotherapy, in which a chemotherapy drug is applied as a cream to the penis. This type of chemotherapy differs from systemic chemotherapy, in which drugs flow through the bloodstream.

Another type of topical therapy uses the drug imiquimod, which helps the person’s own immune system attack cancer cells.

Topical therapies may cause skin irritation. However, other topical medicines may be prescribed to relieve this symptom.

Radiation Therapy: Radiation therapy employs high-energy rays to destroy cancer cells or slow their growth. It is often used when surgery isn’t an option or to remove remaining cancer cells post-surgery. There are two methods:

  • External radiation. Radiation is delivered from outside the body using a special machine.
  • Internal radiation (brachytherapy). Radiation is contained in pellets or delivered through needles, wires, or catheters. It is then placed in or near the cancer itself.

Chemotherapy: Systemic chemotherapy plays a critical role in treating advanced penile cancer, especially when the disease has spread beyond the penis. With this treatment, men are given chemotherapy drugs by mouth or through an injection. The drugs then travel throughout the body.

Patients usually have chemotherapy in cycles that last a few weeks. They have treatments, a rest period, then treatments, then another rest period, and so on.

Chemotherapy can shrink tumors, relieve symptoms, and improve survival rates.

The treatment of penile cancer has seen significant advancements, with a focus on preserving quality of life while effectively combating the disease. Each treatment plan is tailored to the individual, considering not just the cancer’s characteristics but the patient’s preferences and overall health.

Penile Cancer Treatment Side Effects

Addressing the side effects of penile cancer treatment is crucial for patients to navigate their recovery path with dignity and strength. Healthcare teams understand the complexities involved in treating penile cancer, not just from a medical standpoint but also considering the profound emotional and physical impacts it can have on patients.

Physical Side Effects of Penile Cancer Treatment

The treatment of penile cancer, depending on the modality used, can lead to a variety of physical side effects. It’s important to recognize these potential effects to prepare and manage them effectively:

Surgical Treatments Side Effects: Post-operative pain, changes in penile appearance or function, and challenges with urination can occur. For more extensive surgeries, adjustments to body image and sexual function are significant concerns. In some cases, rehabilitation and reconstructive surgeries can offer pathways to recovery and adaptation.

Radiation Therapy Side Effects: Patients may experience skin irritation in the treated area, fatigue, and potentially long-term changes in penile tissue that could affect sexual function. Skin care protocols and energy conservation strategies become key components of care.

Chemotherapy Side Effects: Common side effects include nausea, fatigue, hair loss, and increased infection susceptibility. Medications and supportive therapies can help mitigate these effects, maintaining the patient’s quality of life.

Emotional Impacts

Beyond the physical side effects, the emotional and psychological impact of penile cancer and its treatment is profound.

Beyond the physical side effects, the emotional and psychological impact of penile cancer and its treatment is profound. Feelings of anxiety, depression, and concerns about body image are common. The emotional journey can be as challenging as the physical one, necessitating support from mental health professionals, support groups, and open discussions with healthcare providers about any concerns.

The Role of Communication in Side Effect Management

Open and honest communication with the healthcare team helps manage side effects effectively. No concern is too small, and no question is trivial. By discussing potential and experienced side effects:

Personalized Management Strategies can be developed and tailored to each individual’s specific needs, lifestyle, and treatment plan.

Supportive Care options, ranging from physical rehabilitation services to mental health support, can be explored.

Adjustments to Treatment Plans may be possible, optimizing efficacy while minimizing discomfort.

While the side effects of penile cancer treatment can be challenging, there is a multitude of strategies and resources available to manage them so that patients can lead fulfilling lives post-treatment. Penile cancer treatment is a collaborative effort, with a dedicated team of healthcare professionals working to not only treat the cancer but also to support patients through the side effects of treatment.

Coping and Support for Penile Cancer Patients

A patient’s advancement through penile cancer diagnosis, treatment, and beyond is undeniably challenging, touching not just the physical aspects of one’s being but the emotional and psychological as well. Patients should embrace support and understand the role of mental health in the healing process.

The Power of Professional Counseling

Photo of confident focused man having conversation with psychologist

Professional counseling offers a safe space to express fears, concerns, and emotions that accompany a penile cancer diagnosis and subsequent treatment. Counselors specialized in helping patients undergoing cancer treatment can provide coping strategies, emotional support, and therapeutic interventions to manage anxiety, depression, and stress related to treatment and its side effects. Seeking professional counseling is a proactive step toward maintaining mental well-being.

Finding Strength in Support Groups

Support groups present a unique avenue for connection and understanding among those with similar experiences. These groups offer an environment of empathy, shared stories, and mutual encouragement. Whether in-person or online, support groups enable patients to exchange practical advice on managing side effects, discuss emotional challenges, and celebrate milestones in recovery. The shared experiences within these groups can significantly diminish feelings of isolation, reinforcing that one is part of a community that understands and supports each other.

The Importance of Mental Health in Healing

Attending to one’s mental health is a crucial part of the healing process. It influences one’s outlook on treatment, promotes resilience in the face of challenges, and improves overall quality of life. Patients are encouraged to communicate openly with their healthcare providers about their emotional well-being, explore mental health support options, and actively seek resources that cater to their psychological needs.

Penile Cancer and Sexuality

Sexuality is understandably a significant concern for men with penile cancer. Most men find that they can still enjoy intimacy.

Radiation therapy and chemotherapy may affect erections temporarily. However, these issues usually get better after treatment.

Sexual function after surgery depends on the extent of the surgery. Men who undergo excision, glansectomy, or partial penectomy may still enjoy penetrative intercourse. Individuals who have undergone total penectomy may need to explore alternative methods of intimacy. Some men are able to have their penis reconstructed.

Penile Cancer Prevention and Screening

So can penile cancer be prevented? While there’s no guaranteed way to stop it from developing, there are definitely steps a man can take to lower his risk:

The Shield of HPV Vaccination

The Human Papillomavirus (HPV) is linked to a variety of cancers, including penile cancer. Vaccination against HPV is a powerful tool in preventing cancer. The HPV vaccine is recommended for boys and girls. It is ideally administered before they become sexually active to maximize its protective effects against the high-risk strains of the virus known to cause cancer. For men, receiving the HPV vaccine can significantly reduce the risk of penile cancer by preventing the initial viral infection that can lead to cellular changes in the penis. Embracing HPV vaccination is a forward step in cancer prevention, safeguarding not only individual health but also contributing to the overall reduction of HPV-related cancers in the population.

Circumcision in Infancy

Some experts believe that circumcising baby boys might help protect them from getting penile cancer when they grow up. Studies have shown that men who were circumcised as babies have a lower chance of getting penile cancer later in life compared to men who weren’t circumcised. However, getting circumcised as an adult doesn’t seem to lower the risk as much.

Penile cancer is extremely rare in the United States, even among uncircumcised men. The American Academy of Pediatrics says that the health benefits of circumcising baby boys are greater than the risks, but they also say that these benefits aren’t significant enough to advise circumcision for all newborn boys. In the end, the decision to circumcise is a personal one that often depends more on social and religious factors than on medical evidence.

The Role of Good Hygiene

Maintaining good genital hygiene is another way to reduce the risk of penile cancer. Regular washing of the penis and the foreskin for uncircumcised men helps to prevent the build-up of smegma. This substance can cause irritation and inflammation of the penile tissues, potentially increasing the risk of cancer. Good hygiene practices are simple yet effective measures that men can incorporate into their daily routines that offer a layer of protection against the development of penile cancer.

Stopping the Use of Tobacco Products to Lower Penile Cancer Risk

Stopping the use of tobacco products is a preventative strategy against numerous health conditions, including penile cancer. Using tobacco, whether by smoking or chewing, significantly raises the risk of developing penile cancer. Quitting smoking has immediate and long-term benefits for cancer prevention. Within hours of stopping, the body begins to repair the damage caused by smoking. Long-term, the risks of cancer continue to decrease. For penile cancer, the carcinogenic effects of tobacco can be significantly mitigated by cessation, potentially reducing the risk of developing this type of cancer.

The Importance of Regular Check-Ups for Early Detection

Regular medical check-ups can help detect penile cancer early. During these visits, healthcare providers can look for any signs of abnormalities or changes that could indicate the presence of cancer or precancerous conditions. Men are encouraged to perform self-examinations and promptly report any concerns, such as lumps, sores that do not heal, or changes in the color or texture of the skin. Early detection of penile cancer significantly enhances treatment outcomes and survival rates.

Other Prevention Strategies

  • Having safe sex. Using condoms and dental dams can lower transmission of HPV and HIV, the virus that causes AIDS.
  • Covering the genitals during PUVA treatment. Men who have PUVA treatment for psoriasis should make sure their genitals are covered to avoid radiation exposure.

Penile Cancer Research

The quest for advanced treatments and diagnostic tools for penile cancer is unfolding. Recent research efforts have focused on targeted therapies, immunotherapy, and enhanced diagnostic technologies.

Targeted Therapies: Aiming with Precision

One of the most promising areas of penile cancer research involves targeted therapies. These treatments are designed to identify and attack specific cancer cell markers while sparing healthy tissue, offering a more personalized approach to cancer care. Ongoing research is focused on understanding the genetic and molecular landscapes of penile cancer to identify targets for these therapies. Scientists are working to unravel the complexities of the disease at a molecular level with the hope of developing new drugs that can more precisely target cancerous cells without the broader side effects of conventional chemotherapy.

Immunotherapy: Harnessing the Body’s Defense

Immunotherapy is a cancer treatment that leverages the body’s immune system to fight cancer. This area of research holds particular promise for penile cancer, where treatments such as checkpoint inhibitors can potentially enhance the immune system’s ability to detect and destroy cancer cells. Scientists are exploring various immunotherapy agents, aiming to identify those that are most effective in treating penile cancer. The prospect of immunotherapy offers hope for improved survival rates and a better quality of life for patients.

Advancing Diagnostic Tools: The Key to Early Detection

Early detection is critical in the battle against penile cancer since it significantly impacts treatment outcomes and survival rates. Researchers are dedicating efforts to develop and refine diagnostic tools to detect penile cancer at its earliest stages. Innovations in imaging technologies and molecular diagnostics, including biomarkers in blood or tissue samples, are areas of investigation. By improving our ability to identify penile cancer early, we can enhance treatment efficacy and offer patients a greater chance of a successful outcome.

Summary

While penile cancer remains a rare malignancy, its impact on men’s health and well-being cannot be overstated. It is important for men to be aware of the risk factors and symptoms associated with penile cancer and to seek medical advice early for the best possible prognosis. As research progresses, the future holds promise for even more refined treatments and increased survival rates.

Resources

American Cancer Society

“Chemotherapy for Penile Cancer”
(Last revised: June 25, 2018)
https://www.cancer.org/cancer/types/penile-cancer/treating/chemotherapy.html

“HPV and Cancer”
(Last revised: July 30, 2020)
https://www.cancer.org/cancer/risk-prevention/hpv/hpv-and-cancer-info.html

“Signs and Symptoms of Penile Cancer”
(Last revised: June 25, 2018)
https://www.cancer.org/cancer/types/penile-cancer/detection-diagnosis-staging/signs-symptoms.html

“Living as a Penile Cancer Survivor”
(Last revised: June 25, 2018)
https://www.cancer.org/cancer/types/penile-cancer/after-treatment/follow-up.html

“Local Treatments (Other than Surgery) for Penile Cancer”
(Last revised: June 25, 2018)
https://www.cancer.org/cancer/types/penile-cancer/treating/topical-therapy.html

“Risk Factors for Penile Cancer”
(Last revised: June 25, 2018)
https://www.cancer.org/cancer/types/penile-cancer/causes-risks-prevention/risk-factors.html

“Surgery for Penile Cancer”
(Last revised: June 25, 2018)
https://www.cancer.org/cancer/types/penile-cancer/treating/surgery.html

American Academy of Pediatrics

“Circumcision: Where We Stand”
(Last revised: February 12, 2024)
https://www.healthychildren.org/English/ages-stages/prenatal/decisions-to-make/Pages/Where-We-Stand-Circumcision.aspx

Cancer Research U.K.

“Sex and relationships with penile cancer”
(Last reviewed: January 18, 2021)
https://www.cancerresearchuk.org/about-cancer/penile-cancer/living-with/sex-relationships

Cleveland Clinic

“Penile Cancer”
(Last reviewed: May 19, 2022)
https://my.clevelandclinic.org/health/diseases/6181-penile-cancer

Healthline.com

Purdie, Jennifer
“Common Types of Human Papillomavirus (HPV)”
(Updated: June 26, 2023)
https://www.healthline.com/health/sexually-transmitted-diseases/hpv-types

National Cancer Institute

“Penile Cancer Treatment (PDQ®)–Patient Version”
(Updated: May 12, 2023)
https://www.cancer.gov/types/penile/patient/penile-treatment-pdq

Urology Care Foundation

“Penile Cancer”
(no date)
https://www.urologyhealth.org/urology-a-z/p/penile-cancer

UpToDate

Pettaway, Curtis A., MD, and Pagliaro, Lance C., MD
“Carcinoma of the penis: Surgical and medical treatment.”
(Topic last updated: October 23, 2023)
https://www.uptodate.com/contents/carcinoma-of-the-penis-surgical-and-medical-treatment

Stecca, C.E., Alt, M., Jiang, D.M. et al. Recent Advances in the Management of Penile Cancer: A Contemporary Review of the Literature. Oncol Ther 9, 21–39 (2021).
https://doi.org/10.1007/s40487-020-00135-z


Peyronie’s Disease

Peyronie’s disease occurs when areas of hard scar tissue called plaques form on your penis, just below the surface of the skin. In fact, you might be able to feel them.

Peyronie's disease causes a distinct bend in the penis that can make erections painful and sex difficult.

Technically, the plaques form on the tunica albuginea, the “wrapping” that surrounds the erectile chambers, your corpora cavernosa (two spongy cylinders that fill with blood when you have an erection). The corpora cavernosa sit “on top” of the urethra and the surrounding corpus spongiosum where urine and semen flow. The tunica albuginea that covers the corpus spongiosum is not as thick as that covering the erectile chambers.

When plaques form, the penis becomes less flexible, and you might notice a distinct bend in your penis when it’s erect. Sometimes, the curve is slight and not much of a problem. But in other cases, it’s severe enough to make intercourse difficult. Some men with Peyronie’s disease can’t have intercourse at all.

Fortunately, there are treatments available, and we’ll go over all your options with you.

What causes Peyronie’s disease?

Scientists aren’t completely sure what causes Peyronie’s disease, but many experts believe it’s a wound healing disorder. In other words, you might have injured your penis and it’s having trouble healing. How might an injury happen? It could be from especially energetic sex that might bend your penis. But it can also happen if you’ve had some kind of penile trauma, such as from an accident or a sport injury.

Men with connective tissue disorders (such as Dupuytren’s contracture) may be at higher risk for developing Peyronie’s disease. It might also run in families.

Some men with Peyronie's disease also have Dupuytren's contracture.

What are the symptoms of Peyronie’s disease?

The curved penis and plaques are the most obvious symptoms of Peyronie’s disease

The curved penis and plaques are the most obvious symptoms of Peyronie’s disease, but there are others as well:

  • Deformities. Extensive plaques all around the tunica albuginea can make the penis shaft look indented in the middle, like an hourglass – i.e., an “hourglass” deformity. If the tip of the penis is narrower, it’s called a “bottleneck” deformity. If the base (closest to the body) is narrower, it’s called a “cobra head” deformity. There might also be a “hinge” effect that causes the penis to be unstable when erect.
  • Bumps on the penis. Because of the plaques beneath the skin, the surface of the penis can become bumpy.
  • Pain during erections.
  • Weak erections.
  • Erectile dysfunction.
  • Trouble with intercourse.
  • Penile shortening.

Peyronie’s disease can affect men emotionally and psychologically, too. Having a sexual problem can be distressing. You may feel embarrassed by the curve and anxious about the cause. If you have a partner, you may worry about your ability to sexually satisfy them. If you don’t, you may have concerns about dating and sex with a new partner. If you sense changes in your relationships, you may feel depressed, confused, or frustrated.

Many men with Peyronie’s disease don’t seek treatment because they feel ashamed. But remember, as urologists, we see a lot of delicate conditions, and are here to help.

Note that Peyronie’s symptoms typically emerge over time. It can be helpful to consider Peyronie’s occurring in stages.

What are the stages of Peyronie’s disease?

The treatment path we take depends on the stage of your Peyronie’s disease.

Peyronie’s disease typically progresses in two stages: active and stable.

During the active stage, symptoms start developing. Some common characteristics of the active stage are:

  • Glandular pain or discomfort, with or without an erection.
  • Penile curvature.
  • Penile buckling during intercourse.
  • Other deformities, such as penile shortening, narrowing, indentation, hinge effect, or hourglass effect.
  • Painful erections.
  • Difficulty getting an erection.
  • Psychological and emotional distress.

The active stage usually lasts between 5 and 7 months, but may be longer for some men. Your symptoms can change during this time, too.

By the stable stage, the situation settles down. In fact, we consider you in the stable phase once your symptoms have remained unchanged for at least 3 months. Here’s what you might expect during the stable stage:

  • Plaques stop forming, but they can still be detected in a physical exam or through an ultrasound.
  • Penile deformities, including curvature, don’t worsen. For example, if your penis starts narrowing during the active phase, it shouldn’t narrow any further during the stable phase.
  • You may still have pain, but it might be less frequent or severe.
  • Getting and keeping an erection may still be difficult.
  • Intercourse may be difficult due to pain and penile deformity.
  • Psychological and emotional distress may continue.

It may take 12 months or even longer to have stable disease.

Peyronie's disease - scarring that affects the penis - usually occurs in two stages: acute and chronic.

How is Peyronie’s disease diagnosed?

When you come see us, we’ll start by asking you about your medical history, especially about your penis health. We’ll want to know if you have any pain or distress. We’ll also ask you about sex and whether you can penetrate a partner. These questions might sound intrusive, but the answers help us determine the right treatment path for you. So it’s important to be completely candid with us.

We’ll also do a physical exam and check your penis for plaques. We will also plan an intracavernosal injection test (also called an ICI test). For this test, we’ll inject medicine that induces a short-term erection. Since the curve associated with Peyronie’s disease happens when your penis is erect, the ICI test will give us a clearer picture of your situation. (Note: The ICI test might not occur at the same time as your physical exam.)

You might also have a duplex Doppler ultrasound. This imaging test uses sound waves to show us where the plaques are and how well blood is flowing in your penis.

It might help us to take pictures of your penis, too. Photographs can help us monitor your progress. Rest assured that we will never take photos without your permission, and any photos we do take will remain private and secure.

How is Peyronie’s disease treated?

Do all men with Peyronie’s disease need treatment? Not necessarily. If you’re situation isn’t causing you any distress and you can still have intercourse, you may decide to wait and see what happens. Also, some cases of Peyronie’s disease resolve on their own. This isn’t that common; it happens in about 13% of men. But for this reason, we usually start with more conservative treatments during the acute stage.

Treatment options include injections, traction therapy, Shock Wave Therapy, and surgery

Injections

Injections have a good track record for success in many men. Medicine is injected directly into the plaque. You’ll be given a numbing agent beforehand, so you shouldn’t feel much. The specific medication we’ll inject will depend on the particular characteristics of your case.

Collagenase clostridium histolyticum (CCH)

This treatment is typically used for men who have stable disease and curvature between 30 and 90 degrees. In the United States, CCH injection therapy is marketed under the name of Xiaflex®.

Collagenase is an enzyme that helps your body heal wounds. As a Peyronie’s treatment, it can help break down the plaques on the tunica albuginea.

This route takes time. We generally give CCH injections in cycles over the span of several months. During the first cycle, you might have 2 injections during one week. Then, you’ll take a 6-week break with no injections. Then, you’ll have another 2-injection cycle, take another break, and so on. Most men receive 4 cycles, but additional cycles can be scheduled as needed.

Sometimes, CCH treatment is combined with a technique called modeling. At this time, we’ll gently stretch the penis into a straight position with our hand and hold it in place for 30 seconds. We might give you modeling exercises to do at home, too. We’ll teach you how to do them.

Side effects of CCH injections may include bruising, swelling, pain. Penile fracture, while not common, is also possible. Call us immediately (or go to your local emergency department) if you hear a “popping” sound or experience severe pain, bruising, swelling, difficulty urinating, or a sudden inability to maintain an erection.

Interferon

Interferon is a protein that may break down the plaques. Side effects of this approach are sinus infections, flu-like symptoms, and minor swelling.

Verapamil

Verapamil is a drug that is usually used to treat high blood pressure. Side effects of this treatment include bruising, dizziness, nausea, and pain at the injection site.

Penile Stretching Devices (Traction Therapy)

Some men benefit from penile stretching devices, either on their own or in conjunction with other treatments. (This method is also called traction therapy.) Specific instructions depend on the model used, but typically men wear the device on their penis for a specified period of time, from 30 minutes to several hours. The stretching device pulls the penis into a straight position and holds it in place. Studies have shown penile stretching to be safe and effective, with few side effects. We will show you how to use your device correctly.

One example of a penile traction device is Restorex. This device allows you to straighten the penis and bend it in the opposite direction of your Peyronie’s curve. The device clamps on to the flaccid (not erect) penis, and you control the amount of traction and bending desired. If you use Restorex, you’ll start your traction session by wearing the device in a straight position. After a specified time (up to 15 minutes), you’ll adjust it to an angled position. Depending on your situation, you may have up to an hour of therapy time each day (for example, two 30-minute sessions). For greater comfort, you might wrap your penis with gauze before clamping the device.

It can take some time to get used to using a penile traction device, but don’t get discouraged. We are here to answer all your questions.

Shock Wave Therapy

Another option for treating Peyronie’s-related pain is extracorporeal shock wave therapy (ESWT). With this approach, urologists use a special device to deliver shock waves to the plaques. (Extracorporeal means “outside the body.” The device will be outside your body at all times.) Past studies have reported side effects like pain during treatment, hematoma (similar to a bruise), and petechiae (small, round purple spots that form on the skin when small blood vessels bleed). However, these side effects went away on their own.

Surgery

If your curvature is severe, you might need surgical treatment. Typically, surgery is not recommended until Peyronie’s enters the chronic stage, when symptoms have stabilized. This could be several months after your diagnosis.

Depending on your situation, we may recommend one of these 3 surgical approaches:

Tunical plication

This method involves placing sutures on the plaque-free side of your penis to straighten it. There are a couple of ways to do this. One is to cut out a small piece of tissue and stitch the area closed. Another is to fold over the tissue and suture it in place. Both of these techniques pull the penis into a straight position. The advantage of this technique is that the erection’s quality is not typically affected. The disadvantage is that although the penis gets straightened, the side without the plaque gets shortened to make it the same size as the affected side.

Incision/excision and grafting

With this technique, we cut into the plaque and stretch the penis out. Then, we fill the area with tissue called a graft. Graft material might come from another part of your body or from an animal. We might also use a synthetic material as a graft. The grafting approach is usually recommended for men with more severe cases of Peyronie’s disease. The advantage is that length is preserved. The disadvantage is that there is a higher rate of future erection problems or, rarely, sensory changes, as compared with the plication techniques.

Penile prostheses (implants)

A prosthesis is a medical device that allows you to have an erection. If you’ve developed erectile dysfunction, this might be an option for you.

During an implant procedure, we place inflatable cylinders that get filled with saline into the corpora cavernosa (the spongy cylinders in your penis that normally fill with blood to make a firm erection. In this way, the penis stays erect. The penis can be straightened during the operation after placement of the cylinders (modeling procedure). We also place an easy-to-access pump in your scrotum.

When you want to have an erection, you simply press a button on the pump, and the cylinders inflate with fluid that is stored in a special reservoir. When you are finished with sexual activity, you can press the button again and the cylinders deflate.

The process might sound cumbersome, but most men are highly satisfied with their prostheses. For many men, sexual sensations, orgasm, ejaculation don’t change, and sexual partners often can’t tell that a man has a prosthesis.


After your surgery, we’ll give you detailed information on what you can expect during recovery and when you can have intercourse again. If you have any questions, just give us a call.


Resources

American Urological Association

“Peyronie’s Disease (2015)”
(Published: 2015)
https://www.auanet.org/guidelines/peyronies-disease-guideline

HealthCommunities.com

“Basics of Peyronie’s Disease”
(Last modified: September 29, 2015)
https://web.archive.org/web/20200206181531/http://www.healthcommunities.com/peyronies-disease/overview-of-peyronies.shtml

International Society for Sexual Medicine

“Girth Changes May Not Bother Men With Peyronie’s Disease”
(August 16, 2020)
https://www.issm.info/news/sex-health-headlines/girth-changes-may-not-bother-men-with-peyronies-disease/
“Generally, how satisfied are men with their penile implants?”
https://www.issm.info/sexual-health-qa/generally-how-satisfied-are-men-with-their-penile-implants/

The Journal of Sexual Medicine

Alom, Manaf, MBBS, et al.
“Efficacy of Combined Collagenase Clostridium histolyticum and RestoreX Penile Traction Therapy in Men with Peyronie’s Disease”
(Full-text. Published: April 4, 2019)
https://www.jsm.jsexmed.org/article/S1743-6095(19)30432-1/fulltext
Joseph, Jason, MD, et al.
“Outcomes of RestoreX Penile Traction Therapy in Men With Peyronie’s Disease: Results From Open Label and Follow-up Phases”
(Full-text. Published: November 20, 2020)
https://www.jsm.jsexmed.org/article/S1743-6095(20)30939-5/fulltext

Mayo Clinic

“Peyronie’s disease – Diagnosis & treatment”
(April 4, 2020)
https://www.mayoclinic.org/diseases-conditions/peyronies-disease/diagnosis-treatment/drc-20353473

MedlinePlus

“Duplex ultrasound”
(Page last updated: January 5, 2021)
https://medlineplus.gov/ency/article/003433.htm

Sexual Medicine Reviews

Krieger, Jordan R., MD, et al.
“Shockwave Therapy in the Treatment of Peyronie’s Disease”
(Full-text. Published: March 26, 2019)
https://www.smr.jsexmed.org/article/S2050-0521(19)30007-1/fulltext

Sexual Medicine Society of North America

“Having CCH Injections for Peyronie’s Disease? Don’t Give Up!”
https://www.smsna.org/patients/news/having-cch-injections-for-peyronie-s-disease-don-t-give-up

Up To Date

Khera, Mohit, MD, MBA, MPH
“Patient education: Sexual problems in men (Beyond the Basics)”
(Last updated: February 10, 2020)
https://www.uptodate.com/contents/sexual-problems-in-men-beyond-the-basics

Urology Care Foundation

“What is Peyronie’s Disease?”
(Updated: September 2020)
https://urologyhealth.org/urology-a-z/p/peyronies-disease


Premature Ejaculation

Lots of men are concerned about how long it takes for them to ejaculate. Premature ejaculation (PE) is one of the most commonly reported sexual issues for men. Experts estimate that up to one-third of men experience PE to some degree. Yet many feel embarrassed or ashamed about it.

The good news is that PE is treatable. Many men with PE have success with sex therapy, medications, or a combination of these two strategies.

Stylized text: Premature Ejaculation

What is premature ejaculation?

The International Society for Sexual Medicine (ISSM) describes three components of PE:

  • The time between penetration and ejaculation is “too short” (according to what the man wishes)
  • The man feels that he cannot control when he ejaculates.
  • There are feelings of distress.

How short is “too short”? That depends. The desired time frame can be different for every couple. One couple may enjoy five minutes of penetration; another may be completely satisfied with two. As long as both partners are satisfied, there is no “right” time frame.

However, that lack of control—and distress—are important components. Men with PE may feel frustrated and worry about satisfying their partner. Their partners may feel disappointed or worry about their relationship. Single men may shy away from starting new relationships because they’re anxious about ejaculating quickly. Others feel that PE calls their masculinity into question.

Most research on PE focuses on heterosexual and vaginal sex, and the discussion below is based on that research. However, the information may not necessarily apply to gay men, bisexual men, or men who have non-vaginal sex (such as mutual masturbation or oral sex). More research is needed on PE outside of heterosexual vaginal sex contexts.

What’s the official definition of premature ejaculation?

PE is categorized by how long it’s been a problem. The American Urological Association (AUA) explains it in this way:

  • Lifelong PE occurs when a man ejaculates within the first two minutes of penetrative sex, has trouble controlling ejaculation, and feels distress. This has been the situation since his first experience with sexual intercourse.
  • Acquired PE happens after a man has had some sexual experience. In the past, ejaculatory time frames haven’t been a problem. But now, he ejaculates before he wishes to, has trouble controlling ejaculation, and feels distress.

In some cases, PE happens only with certain partners or in certain situations.

In some cases, PE happens only with certain partners or in certain situations. For example, some sexual problems occur when couples don’t think there’s enough privacy or time for sex.

The ISSM also describes three other situations that are similar to PE:

  • Antes portas ejaculation. The term antes portas is Latin for “before the gates.” Men with this condition ejaculate before penetration starts.
  • Natural variable PE. Men have early ejaculations from time to time, but not with a consistent pattern. The ISSM calls this “a variant of normal experience.”
  • Subjective PE. Men with subjective PE think they ejaculate earlier than other men, but do so in in a time frame of five minutes or more.

What causes premature ejaculation?

Psychological causes

Premature ejaculation often has psychological causes:

Relationship issues. The couple may have conflicts to resolve. Or the man may feel unhappy or insecure in his current relationship.

Depression. Depression can affect sexual relationships in many ways; PE is one of them.

Anxiety and lack of confidence. A man may not feel secure in his ability to please a partner sexually, especially if he has limited sexual experience or a negative body image. This nervousness may lead him to ejaculate before he wishes to.

Feeling guilty about sex. Beliefs that sex is bad or dirty can be deep-rooted and affect performance.

Serotonin

Some researchers think that the neurotransmitter serotonin might be involved with PE. Higher amounts of serotonin have been linked to longer ejaculation times, while lower amounts have been linked to shorter times.

The good news is that PE is treatable

How is premature ejaculation diagnosed?

To diagnose PE, urologists start with a physical exam to make sure the reproductive system is in good working order.

Urologists also ask questions about the man’s medical history, sexual history, and current relationship. Some questions may seem highly personal, but honest answers allow doctors to develop the best treatment plan.

Such questions may include the following:

  • How long does it typically take for you to ejaculate?
  • How long have you been experiencing PE?
  • Does it happen all the time?
  • Does it happen with some partners but not others?
  • If you have a partner, has this situation affected your relationship?
  • If you are single, does the situation prevent you from starting new sexual relationships?
  • Do you have any pain or discomfort?

How is premature ejaculation treated?

Once PE has been diagnosed by a healthcare professional, men have a few treatment options they can try. Some involve medications; others involve behavioral therapy. Using a combination of medication and therapy may be even more effective.

Once PE has been diagnosed by a healthcare professional, men have a few treatment options they can try.

A man taking medication

Medications

Currently, no drugs have been approved for the treatment of PE in the United States. But doctors sometimes prescribe certain drugs for “off label” purposes. This means that while the drugs haven’t been approved for a specific condition, medical professionals have found them to be helpful for some patients. Options include the following:

Numbing creams and sprays. These products are applied to the tip of the penis about a half hour before sex to reduce sensation. They are then washed off 5 to 10 minutes before sex.

Selective serotonin reuptake inhibitors (SSRIs). These drugs, such as fluoxetine and sertraline, increase the amount of serotonin in the brain. They are antidepressants, but some doctors prescribe them for PE. They are usually taken every day.

Clomipramine. This drug is a tricyclic antidepressant commonly prescribed to treat obsessive compulsive disorder. However, it also works by increasing serotonin levels in the brain. It is usually taken before sex.

Tramadol. An opioid usually prescribed for pain, tramadol can also affect serotonin levels. It needs to be used carefully, as it can be habit-forming.

Alpha blockers (full name: alpha-1 adrenergic receptor antagonists). These drugs are used to treat an enlarged prostate. And while they can delay ejaculation in men with PE, they can affect ejaculation in other ways, too. For example, men taking alpha blockers might have retrograde ejaculation (when semen travels backward into the bladder instead of forward out of the penis) or anejaculation (being unable to ejaculate at all).

Note: Alpha blockers may interact with erectile dysfunction drugs, so men should let their doctors know if they are using either.

Sex Therapy

Working with a sex therapist, alone or with a partner, can have great benefits for men with PE.

Men can review their expectations of sex. Movies and internet videos often show sex lasting a long time, but in reality, time frames vary widely. According to the ISSM, the average time between penetration to orgasm is about five minutes.

A woman hugs her male partner from behind

Couples can build their communication skills, especially when they’re talking about sex. Single men can also learn strategies for having sexual conversations with new partners.

Men can learn techniques to hold off ejaculation during masturbation or partnered sex:

  • The squeeze method:

    • This technique helps men recognize the sensations that come before ejaculation.
    • It involves stimulating the penis until the man is just about to ejaculate.
    • Then, the man or his partner squeezes the penis tip and stops stimulation for about 30 seconds.
    • The process is repeated until the man wishes to ejaculate.

  • The stop-start method:

    • With this method, the man or his partner stimulates his penis until he’s about to ejaculate.
    • At that point, they stop the stimulation for about 30 seconds, until the feeling passes.
    • Then, the stimulation continues again.
    • These steps can be repeated until the man feels ready to ejaculate.

Other strategies for delaying ejaculation

These methods may also be helpful:

  • Distraction. Some men try to think of other things—work, a soccer game, the stock market, or some other non-sexual topic—if they are about to climax before they wish to.
  • Masturbation before partnered sex. Some men masturbate and ejaculate first and then have sex with a partner. The second orgasm might take more time to reach than the first.
  • Wearing a condom. A condom might make the penis less sensitive—not enough to reduce pleasure, but enough to delay ejaculation.

Don’t give up

Premature ejaculation can be frustrating, and treatment might take some trial and error. However, many men find that their ejaculatory control, sexual satisfaction, and confidence improve with patience, time, and treatment.

Resources

American Urological Association

Shindel, Alan W., et al.
“Disorders of Ejaculation: An AUA/SMSNA Guideline (2020)”
(Published in the Journal of Urology: March 1, 2022)
https://www.auanet.org/guidelines-and-quality/guidelines/disorders-of-ejaculation

Cleveland Clinic

“Alpha-blockers”
(Last reviewed: January 18, 2022)
https://my.clevelandclinic.org/health/treatments/22321-alpha-blockers

Harvard Health Publishing / Harvard Medical School

“Which drug for erectile dysfunction?”
(August 9, 2022)
https://www.health.harvard.edu/mens-health/which-drug-for-erectile-dysfunction

International Society for Sexual Medicine

“How can a man effectively delay ejaculation?”
https://www.issm.info/sexual-health-qa/how-can-a-man-effectively-delay-ejaculation

“ISSM Patient Information Sheet on Premature Ejaculation”
(2015)
https://www.issm.info/media/attachments/2021/08/17/03-clinical-guidelines—issm-patient-information-sheet-on-pe—vjan-2015.pdf

Mayo Clinic

“Alpha blockers”
(September 3, 2021)
https://www.mayoclinic.org/diseases-conditions/high-blood-pressure/in-depth/alpha-blockers/art-20044214

MedlinePlus

“Clomipramine”
(Last revised: September 15, 2018)
https://medlineplus.gov/druginfo/meds/a697002.html

“Tramadol”
(Last revised: January 15, 2022)
https://medlineplus.gov/druginfo/meds/a695011.html

Sexual Medicine

McNabney, Sean M., MS, et al.
“Are the Criteria for the Diagnosis of Premature Ejaculation Applicable to Gay Men or Sexual Activities Other than Penile-Vaginal Intercourse?”
(Published: April 24, 2022)
https://academic.oup.com/smoa/article/10/3/1/6825599

Translational Andrology and Urology

Hisasue, Shin-ichi
“The drug treatment of premature ejaculation”
(Full-text. Published: August 1, 2016)
https://tau.amegroups.com/article/view/10984/11770

Urology Care Foundation

“Premature Ejaculation”
(Updated: July 16, 2020)
https://www.urologyhealth.org/urology-a-z/p/premature-ejaculation


Prostate Cancer

Prostate cancer. About 1 in 8 men will develop this disease during their lifetime, according to the American Cancer Society. And it’s the second most common cancer in men. (Lung cancer is the first.)

So when a man hears that he or a loved one has prostate cancer, it’s natural to have questions and concerns. What does the diagnosis really mean? What will treatment be like? What will happen to quality of life?

Illustration of prostate cancer in male anatomy
Male Prostate Cancer diagram illustration

The following overview can answer many questions people have about prostate cancer.

What is the prostate?

The prostate is a small gland located under the bladder and in front of the rectum. The urethra—the tube that carries urine and semen out of the body—runs through the middle.

The prostate makes prostatic fluid, a substance that mixes with sperm cells and other fluids to form semen. Prostatic fluid nourishes sperm cells and helps them move out of the urethra and toward an egg cell for fertilization.

When a man has prostate cancer, abnormal cells grow and form tumors. Sometimes, cancer cells stay within the prostate gland. But they can also spread to other parts of the body. This process is called metastasis.

Prostate cancer is typically classified by how far it has spread.

About 1 in 8 men will develop [prostate cancer] during their lifetime.

  • Localized prostate cancer. Cancer cells are found only in the prostate gland itself. It has not spread beyond the prostate gland.
  • Localized advanced prostate cancer. Cancer cells have spread to nearby tissues outside the prostate.
  • Advanced prostate cancer. Cancer cells have spread to other parts of the body, such as the lymph nodes, bones, liver, or lungs.

What are the risk factors for prostate cancer?

Several factors contribute to a man’s risk for prostate cancer:

  • Age. Men are more likely to develop prostate cancer after age 50. The average age at diagnosis is 66, according to the American Society of Clinical Oncology (ASCO).
  • Family history of prostate, breast, or ovarian cancer. If a man’s brother, father, or grandfather has had prostate cancer, he is at higher risk himself. Risk also increases if he has had a relative with breast or ovarian cancer.
  • Race/Ethnicity. Prostate cancer is more common in non-Hispanic Black men.
  • Weight. Men over 50 who are overweight could be at higher risk.

What are the symptoms of prostate cancer?

Not all men have symptoms at the beginning. And often, symptoms are similar to those of other urological conditions, especially an enlarged prostate. Some of the more common symptoms include:

  • Trouble with urination. Men might have a weak urine flow or need to urinate more often. They may also feel pain or a burning sensation when urinating.
  • Erectile dysfunction.
  • Blood in the urine.
  • Pain or weakness. Pain may occur in the pelvis, lower back, hips, chest or bones. There might also be pain during ejaculation.
  • Weight loss or poor appetite.

When should a man be screened for prostate cancer?

Through regular screening, prostate cancer is often found in an early stage, before symptoms begin.

According to guidelines from the American Urological Association (AUA), men aged 40 to 54 might consider screening if they have prostate cancer risk factors:

  • African American ancestry
  • A family history of prostate cancer (such as in a brother, father, or grandfather)
  • Prostate cancer symptoms, such as problems with urination

The AUA suggests that men between the ages of 55 and 69, no matter what their risk, discuss screening with their doctor.

Screening is not generally recommended for men aged 70 and older or men who have a life expectancy of 10 to 15 years. However, healthy men in this age group may decide to continue with prostate cancer screenings.

Not all men have symptoms at the beginning. And often, symptoms are similar to those of other urological conditions

What tests are done to screen for prostate cancer?

Blood sample tube with lab requisition form for PSA test

Screening for prostate cancer usually starts with these tests:

PSA test

PSA stands for prostate-specific antigen, a protein made by both prostate cells and prostate cancer cells. A PSA test measures levels of PSA in the blood. If PSA tests are higher than normal (a common cutoff is 4 ng/dL), a doctor may suggest further testing.

Having a higher-than-normal PSA levels does not mean a man has cancer. Other health conditions, like an enlarged prostate or prostatitis (a prostate infection) can make PSA levels rise. So can certain medicines, recent ejaculation, and recent urologic procedures. Even aging can increase PSA levels.

Men with large prostates may have higher PSA levels also.

Digital rectal exam (DRE)

A DRE is a physical exam that allows a doctor to check the prostate directly. The doctor inserts a gloved, lubricated finger into the rectum and feels for any bumps or other abnormalities on prostate gland itself. A DRE may be a little uncomfortable, but it takes only a few moments.

If a doctor notices anything unusual on a PSA test or a DRE, they may order further testing. Sometimes, this means having another PSA test in a couple of months. It might also mean having imaging tests or a prostate biopsy.

What is a prostate biopsy?

During a prostate biopsy, small amounts of prostate tissue are removed and studied under a microscope. A biopsy is the only test that can confirm a prostate cancer diagnosis. Depending on the method used, a prostate biopsy may take anywhere from 15 to 90 minutes.

Before the biopsy begins, men are given local anesthesia. The doctor may use imaging technology, such as an ultrasound or MRI scan, to guide the process. Typically, they access the prostate in one of two ways:

  • Through a small incision between the anus and scrotum
  • Through the rectum

The doctor uses a needle to collect several tissue samples from the prostate. A specialist then uses a microscope to examine the samples for prostate cancer cells.

What is prostate cancer staging and grading?

If the specialist finds cancer, they will see if the cancer has spread and how fast it is growing. This is done in two ways:

  • Staging. Prostate cancer is classified by stages depending on how large the original tumor is, whether cancer has spread to lymph nodes, and whether cancer has spread to other parts of the body.
  • Grading. Cancer doctors use a measure called a Gleason score to grade prostate cancer. The Gleason score indicates how fast cancer cells are growing and spreading. This score helps doctors learn more about potential risk; it tells doctors whether the cancer is likely to come back after treatment.

How is prostate cancer treated?

When a man is diagnosed with prostate cancer, his doctor will help him make decisions about treatment. Prostate cancer tends to grow slowly, so in many cases, men don’t need to choose treatment right away. They can take some time to research their situation and ask questions.

When choosing a treatment plan, doctors and patients consider several factors:

  • Cancer stage and grade. Some treatments work better for localized cancer. Others are more appropriate for cancer that has spread. Doctors look at how far the cancer has progressed when making treatment suggestions.
  • Age and overall health. Doctors account for a man’s age, other health conditions, and life expectancy.
  • Feelings about treatment. Some men want to treat their cancer immediately. Others choose to wait and see if their symptoms change or if the cancer progresses.

Treatment options can include:

  • Active surveillance
  • Observation/watchful waiting
  • Surgery
  • Radiation
  • Hormone therapy
  • Cryotherapy (cryoablation)
  • Chemotherapy
  • Immunotherapy
  • Focal therapy (HIFU)

Active surveillance

Treatment doesn’t start right away. Instead, patients have regular PSA tests, digital rectal exams, imaging tests, and biopsies to keep track of how the cancer progresses. If it spreads, or if symptoms worsen, then treatment begins.

Men may choose active surveillance if their cancer is slow-growing, and they want to avoid potential treatment side effects like erectile dysfunction and urinary incontinence.

Observation/watchful waiting

This approach is similar to active surveillance. However, there is less testing, and decisions about treatment are based on changes in symptoms.

Surgery

Men with localized prostate cancer may undergo a radical prostatectomy. During this procedure, a surgeon removes the whole prostate gland, the seminal vesicles (glands that make fluid found in semen), and nearby tissue. Lymph nodes may also be removed. As these tissues are removed, cancer cells are removed with them.

Today, the most common surgical approach is the robot-assisted laparoscopic prostatectomy (RALP). A trained surgeon controls the surgery with a computer, but a robot holds and maneuvers the surgical instruments, including a tiny camera.

During a RALP, the surgeon makes several 1- to 2-inch incisions called ports in the abdomen. Ports allow the robot access to the prostate gland.

In some cases, the laparoscopic approach is used without a robot. In this instance, the surgeon holds and maneuvers the instruments.

Rarely, an open prostatectomy is done. Unlike a laparoscopic approach with small incisions, an open approach involves one 8- to 10-inch incision through which the prostate is removed.

Radiation

Radiation uses strong, radioactive rays to kill cancer cells. Radiation oncologists can deliver radiation in a few ways:

External beam radiation therapy (EBRT)

With this method, a special device delivers radiation beams from outside the body. Doctors are careful to target the cancer cells as precisely as possible to avoid risk to nearby healthy tissues.

Brachytherapy

With this type, radiation is administered from inside the body. Tiny radioactive pellets are put directly into the prostate. These pellets may be placed permanently, with the pellets giving off radiation for several weeks or months. Or the pellets may be temporary, giving off higher doses of radiation for a short time period before they are removed.

Because of radiation concerns, men who undergo brachytherapy may need to take precautions. For example, their doctor may tell them to stay away from pregnant women or children while the seeds are active.

Radiopharmaceuticals

Drugs containing radioactive substances may be used to treat prostate cancer, especially if it has spread to the bones. These injected drugs move through the bloodstream and target cancer cells.

Radiation therapy may be combined with hormone therapy, which is explained below.

Hormone therapy (androgen deprivation therapy—ADT)

The hormone testosterone fuels prostate cancer cells. Hormone therapy lowers a man’s testosterone levels so the cancer has less fuel to work with.

Hormone therapy is usually given through medications. These drugs work in different ways. Some prevent the production of luteinizing-hormone-releasing hormone (LHRH), a hormone that “tells” the body to make testosterone. Other drugs prevent testosterone from reaching the cancer cells.

Surgery to remove the testes (the glands that make testosterone) is another option, although it is rarely done in the United States.

Cryotherapy (cryoablation)

With cryotherapy, cancer cells are frozen and destroyed. Men are given anesthesia for this procedure. Using ultrasound imaging as a guide, the doctor uses a needle to deliver cold gasses, targeting the cancer cells.

Chemotherapy

Chemotherapy delivers medication to the entire body through an IV. It can shrink tumors and attack cancer cells that have spread to other parts of the body.

Immunotherapy

This approach uses the man’s own immune system to fight cancer cells. A special vaccine is made from the man’s white blood cells and medications. The final product is then delivered as an infusion.

Focal therapy (high-intensity focused ultrasound—HIFU)

HIFU is a relatively new treatment for prostate cancer. It uses ultrasound waves to heat and destroy cancer cells. The waves are delivered through a probe placed in the man’s rectum. They can be targeted toward cancer cells specifically, reducing the risk of harm to nearby tissues.

What are some side effects of prostate cancer treatment?

A man grimaces while holding his lower back

Side effects are common with prostate cancer treatments. Every man is different, and some treatments may have more side effects than others. Men and their doctors often consider side effects (and their management) when they make treatment decisions.

Erectile dysfunction (ED)

ED happens when a man cannot keep an erection firm enough for sexual activity. It’s especially common after surgery, as the nerves responsible for erections are close to the prostate gland. As much as surgeons try to avoid it, nerve damage can still occur. Radiation can also affect erectile nerves and blood vessels.

Erectile function can recover, but it takes some time. For some men, it takes just a few months. For others, it may take up to two years.

ED is treatable, however, and there are several effective therapies available. Men can try medications, self-injections, suppositories, and vacuum erection devices. In more severe cases, penile implants may be suggested. A man’s doctor can help him decide which treatments are most appropriate. (Learn more about ED and its treatment here.)

Urinary incontinence

Men may have trouble with bladder control after prostate cancer treatment. As a result, they leak urine. This problem is called incontinence. Some examples are:

  • Stress urinary incontinence. A man might leak urine when he coughs, laughs, or exercises.
  • Urge incontinence. The urge to urinate comes on suddenly, and men might leak urine if they cannot get to the bathroom in time.
  • Mixed incontinence. Men with this type have a combination of both stress urinary incontinence and urge incontinence.

Like ED, incontinence can be treated. Sometimes, simple lifestyle changes or bladder training are all that is needed. Other options include pelvic floor exercises (such as Kegel exercises), medications, nerve stimulation procedures, urethral slings, and surgery.

Learn more about urinary incontinence here.

Other side effects

During and after prostate cancer treatment, men may also experience:

  • Bowel control issues
  • Fatigue
  • Nausea
  • Low sex drive
  • Changes in ejaculation (such as no ejaculation or ejaculating smaller amounts of semen)
  • Moodiness
  • Depression
  • Poor appetite
  • Swollen lymph nodes
  • Osteoporosis and increased risk of bone fractures
  • Increased risk of infections

Men are encouraged to discuss side effects with their cancer care team.

Living with prostate cancer

Staying as healthy as possible during prostate cancer treatment is important for maintaining a good quality of life. Eating a healthy diet and getting regular exercise can boost energy levels and emotional wellbeing.

Men need to take care of their mental health as well. Prostate cancer and its treatment can be stressful, and many men feel anxious about the future or depressed about changes in their life. Taking time to relax and enjoy time with friends and family is key. Men may also consider counseling and support groups to help them cope with cancer and treatment side effects. Doctors can offer resources and make referrals.

Resources

American Cancer Society

“About Prostate Cancer”
(Last revised: October 8, 2021)
https://www.cancer.org/content/dam/CRC/PDF/Public/8793.00.pdf

“Immunotherapy for Prostate Cancer”
(Last revised: August 1, 2019)
https://www.cancer.org/cancer/prostate-cancer/treating/vaccine-treatment.html

“Prostate Cancer Risk Factors”
(Last revised: June 9, 2020)
https://www.cancer.org/cancer/prostate-cancer/causes-risks-prevention/risk-factors.html

“Prostate Cancer Stages”
(Last revised: October 8, 2021)
https://www.cancer.org/cancer/prostate-cancer/detection-diagnosis-staging/staging.html

“Signs and Symptoms of Prostate Cancer”
(Last revised: August 1, 2019)
https://www.cancer.org/cancer/prostate-cancer/detection-diagnosis-staging/signs-symptoms.html

“Treating Prostate Cancer”
https://www.cancer.org/content/dam/CRC/PDF/Public/8796.00.pdf

American Urological Association

Carter HB, Albertsen PC, Barry MJ, et al.
“Early Detection of Prostate Cancer (2018)”
(Published: 2013. Reviewed and validity confirmed: 2018)
https://www.auanet.org/guidelines-and-quality/guidelines/prostate-cancer-early-detection-guideline

Eastham JA, Auffenberg GB, Barocas DA, et al.
“Clinically Localized Prostate Cancer: AUA/ASTRO Guideline (2022)”
(Published: 2022)
https://www.auanet.org/guidelines-and-quality/guidelines/clinically-localized-prostate-cancer-aua/astro-guideline-2022

Lowrance WT, Breau RH, Chou R et al.
“Advanced Prostate Cancer: AUA/ASTRO/SUO Guideline (2020)”
(Published: 2021)
https://www.auanet.org/guidelines-and-quality/guidelines/advanced-prostate-cancer

Morgan SC, Hoffman K, Loblaw DA, et al.
“Hypofractionated Radiation Therapy for Localized Prostate Cancer: An ASTRO, ASCO, and AUA Evidence-Based Guideline (2018)”
(Published: 2018)
https://www.auanet.org/guidelines-and-quality/guidelines/prostate-cancer-hypofractionated-radiotherapy-guideline

Pisansky TM, Thompson IM, Valicenti RK et al.
“Adjuvant and Salvage Radiotherapy after Prostatectomy: ASTRO/AUA Guideline (2019)”
(ASTRO/AUA guideline. Published: 2013. Amended in 2018 & 2019)
https://www.auanet.org/guidelines-and-quality/guidelines/prostate-cancer-adjuvant-and-salvage-radiotherapy-guideline

Cancer.net (American Society of Clinical Oncology)

“Prostate Cancer: Statistics”
(December 2022)
https://www.cancer.net/cancer-types/prostate-cancer/statistics

Cleveland Clinic

“High-Intensity Focused Ultrasound (HIFU)”
(Last reviewed: August 31, 2022)
https://my.clevelandclinic.org/health/treatments/16541-hifu-high-intensity-focused-ultrasound

MedicalNewsToday.com

Fletcher, Jenna
“What is a prostate biopsy? The procedure, recovery, results, and more”
(January 18, 2023)
https://www.medicalnewstoday.com/articles/317601

Newman, Tim
“What is the prostate gland?”
(Updated: January 6, 2023)
https://www.medicalnewstoday.com/articles/319859

Memorial Sloan Kettering Cancer Center

“High-Intensity Focused Ultrasound (HIFU) Can Control Prostate Cancer With Fewer Side Effects”
(June 14, 2022)
https://www.mskcc.org/news/high-intensity-focused-ultrasound-hifu-can-control-prostate-cancer-fewer-side-effects

National Cancer Institute

“Cancer Stat Facts: Prostate Cancer”
https://seer.cancer.gov/statfacts/html/prost.html

“Prostate Cancer Screening (PDQ®)–Patient Version”
(Updated: May 6, 2022)
https://www.cancer.gov/types/prostate/patient/prostate-screening-pdq

Prostate Cancer Foundation

“Grading Your Cancer”
https://www.pcf.org/about-prostate-cancer/diagnosis-staging-prostate-cancer/gleason-score-isup-grade/

“Localized or Locally Advanced Prostate Cancer”
https://www.pcf.org/about-prostate-cancer/diagnosis-staging-prostate-cancer/localized-locally-advanced-prostate-cancer/

Urology Care Foundation

“Chemotherapy”
https://www.urologyhealth.org/urology-a-z/p/prostate-cancer-%E2%80%93-advanced/treatment/chemotherapy

“Prostate Cancer – Advanced”
(Updated: September 2021)
https://www.urologyhealth.org/urology-a-z/a_/advanced-prostate-cancer

“Prostate Cancer – Early-Stage”
(Updated: February 2023)
https://www.urologyhealth.org/urologic-conditions/prostate-cancer


Prostatitis

Prostatitis—inflammation of the prostate gland—is a painful condition that can make urination and sexual intercourse difficult. Experts estimate that between 35% and 50% of men develop prostatitis symptoms at some point in their lives. It can happen to men of all ages.

The prostate is a small, walnut-shaped gland located between the penis and the bladder. Part of the urethra (the tube from which urine and semen exit the penis) is surrounded by prostate tissue.

Diagram showing a normal prostate verses on that is red with a bullseye radiating outward

35% ~ 50% of men develop prostatitis symptoms at some point in their lives

The prostate is an important gland for male reproduction. It contracts when a man ejaculates, closing off the pathway between the bladder and urethra so that urine doesn’t mix with semen. It also produces prostatic fluid, which nourishes sperm cells and helps them travel toward an egg after ejaculation.

Types of Prostatitis

Urologists classify prostatitis into 4 types:

  • Acute bacterial prostatitis. Caused by bacteria, this type of prostatitis comes on suddenly, and symptoms can be severe. But with proper treatment, it goes away fairly quickly.
  • Chronic bacterial prostatitis. This type is also caused by bacteria, but symptoms start gradually and tend to be less severe. However, they usually last longer. Men with chronic bacterial prostatitis may have symptoms for several months.
  • Chronic prostatitis/chronic pelvic pain syndrome (CP/CPPS). This is the most common type of prostatitis. It’s not caused by bacteria. In fact, scientists aren’t exactly sure what causes it, but research is ongoing.
  • Asymptomatic inflammatory prostatitis. When an illness is asymptomatic, it doesn’t cause any symptoms. Men might not be aware they have this type of prostatitis. It is often discovered during tests for other urologic conditions. It does not have complications and doesn’t require treatment.

Because asymptomatic inflammatory prostatitis does not need treatment, this article will focus on acute bacterial prostatitis, chronic bacterial prostatitis, and CP/CPPS.

Bacterial Prostatitis

diagram showing where bacterial would cause inflamation of the prostate, with examples of the different bacteria enlarged

What causes bacterial prostatitis?

Both acute and chronic bacterial prostatitis are caused by bacteria. The bacteria may be linked to another infection, such as a urinary tract infection (UTI) or sexually transmitted infection (STI). It might also develop after a urologic procedure, such as catheterization, a biopsy, or surgery.

Bacteria can reach the prostate via the urethra or the bladder. The most common types of prostatitis-causing bacteria are Escherichia coli (E. coli), Proteus species, or staph bacteria. Bacteria from sexually transmitted infections like gonorrhea and chlamydia can also cause bacterial prostatitis.

What is the difference between acute and chronic bacterial prostatitis?

The main difference between the 2 types of bacterial prostatitis is timing.

In medical terms, acute refers to an illness that starts suddenly, could be severe, and resolves relatively quickly. In contrast, a chronic illness develops over time and takes longer to go away.

What are the symptoms of bacterial prostatitis?

Acute and bacterial prostatitis have many symptoms in common:

  • urinating more frequently
  • urinating more urgently
  • pain or discomfort during urination
  • trouble starting urination
  • weak urine stream
  • cloudy urine
  • urinary retention (being unable to empty the bladder)
  • urinary blockage (being unable to urinate)
  • nocturia (having to get up during the night to urinate, interrupting sleep)
  • pain in the genitals or lower abdomen
  • fatigue

Men with acute bacterial prostatitis are more likely to have these symptoms:

Bacterial prostatitis might cause painful ejaculation

  • fever and chills
  • nausea and vomiting
  • body aches

Men with chronic bacterial prostatitis might experience painful ejaculation.

It’s also possible for men with chronic bacterial prostatitis to have no symptoms at all.

Note: Men whose symptoms start suddenly and worsen quickly should see a doctor immediately. Untreated prostatitis can lead to more serious infections, prostatic abscess, and inflammation of the epididymis (the area where sperm cells are stored).

How is bacterial prostatitis diagnosed?

There are several steps involved when diagnosing bacterial prostatitis:

  • Medical history. A doctor will ask questions about symptoms, urologic history, and general health.
  • Urinalysis. A urinalysis is a urine test. A urine sample will be checked for bacteria and any other substances that could be linked to symptoms.
  • Digital rectal exam (DRE). Digital in this case refers to digits—another word for fingers. During a DRE, a doctor will gently place a gloved, lubricated finger into the rectum. This process allows them to check the prostate for any physical abnormalities.
  • Urine culture. A urine culture is another way to test for bacteria and other germs. In this case, the urine sample is placed in a petri dish in a lab. After a few days, a specialist will check the dish and analyze the contents, seeing if any bacteria or other organisms have grown or multiplied.
  • Other tests. Blood, semen, and imaging tests can help doctors rule out other conditions.

How is bacterial prostatitis treated?

Bacterial prostatitis is usually treated with antibiotics. The type of medicine prescribed will depend on the type of bacteria causing the infection.

Most men need to take antibiotics for 2 to 8 weeks. Doctors may prescribe a longer course if they think the infection might return.

Men with severe cases of acute bacterial prostatitis may spend a short time in the hospital. In that setting, they will receive IV (intravenous) antibiotics and fluids. After hospitalization, a man usually needs to take oral (by mouth) antibiotics for up to 4 weeks.

What are the complications of bacterial prostatitis?

If not treated properly, bacterial prostatitis may lead to bacterial infections in other areas, such as the blood and the epididymis (the coiled tube in back of the testicle). Men may also develop chronic back pain or prostatic abscesses.

Chronic Prostatitis/Chronic Pelvic Pain Syndrome (CP/CPPS)

Chronic prostatitis/chronic pelvic pain syndrome (CP/CPPS) affects about 2 percent to 10 percent of adult men worldwide.

What are the symptoms of CP/CPPS?

Men with CP/CPPS often report the following symptoms:

  • Pain in the pelvic area, groin, or genitals. This pain may be sharp or dull, constant or intermittent. For a CP/CPPS diagnosis, the pain must last for at least 3 of the previous 6 months and not be explained by another cause.
  • Urinary symptoms. Like bacterial prostatitis, CP/CPPS can have urinary symptoms, too. Men may need to urinate more frequently or urgently. They might experience pain while they urinate.
  • Sexual symptoms. Some men have difficulty ejaculating or experience pain when they do so.

The severity of CP/CPPS symptoms can vary. Some men go back and forth between flare-ups and times when they’re feeling better.

Men with CP/CPPS don’t usually have a fever.

What causes CP/CPPS?

The exact cause of CP/CPPS isn’t known, but scientists are investigating. Some theories include trauma-related inflammation and autoimmune responses. (Autoimmune pertains to conditions where the body’s immune system attacks healthy tissue.)

Some experts believe psychological stress could be involved with CP/CPPS. Many men find that their symptoms worsen during times of stress.

How is CP/CPPS diagnosed?

There is no one definitive test that can diagnose CP/CPPS. Instead, doctors rule out other health conditions that can have similar symptoms, such as urinary tract infections.

Tests used to assess CP/CPPS symptoms are similar to those used to diagnose bacterial prostatitis, described above:

  • Medical history, assessment of symptoms
  • Digital rectal exam (DRE)
  • Urinalysis
  • Urine culture
  • Other tests (such as blood, semen, or imaging tests)

How is CP/CPPS treated?

Men with CP/CPPS have several treatment options. Sometimes, a combination of treatments is used:

  • Medications. Different medicines can target different CP/CPPS symptoms.
    • Alpha-blockers (example: tamsulosin) help relax muscles near the prostate.
    • Anti-inflammatories (examples: aspirin, ibuprofen) can reduce inflammation and relieve pain.
    • 5-alpha-reductase inhibitors might be prescribed to men who have trouble urinating. However, these drugs might not be the best choice with men concerned about fertility, as they can affect semen volume.
    • Antibiotics aren’t typically prescribed for CP/CPPS because it is not caused by bacteria. However, these drugs do help some men, especially if they have a related bacterial infection.
  • Pelvic floor physical therapy. The pelvic floor is a group of muscles that hold the pelvic organs, such as the bladder, in place. Working with a pelvic floor physical therapist can reduce pain and might improve sexual function. Techniques may include Kegel exercises, relaxation therapies, biofeedback, cooling and warming, and stretching muscles and soft tissues (myofascial release).
  • Cognitive behavioral therapy (CBT). Because stress can worsen CP/CPPS symptoms, some men benefit from a psychological approach called cognitive behavioral therapy. A qualified therapist can suggest ways to cope with CP/CPPS and better manage stress, depression, and anxiety.
  • Acupuncture. Acupuncture is a form of traditional Chinese medicine that uses tiny needles placed through the skin. Some men with CP/CPPS find that acupuncture relieves pain.

Taking Care at Home

During treatment for bacterial prostatitis or CP/CPPS, these steps may ease symptoms:

  • Avoid foods and drinks that irritate the bladder. These may include spicy foods, alcohol, caffeinated drinks (like coffee, tea, and soda), and acidic foods (like citrus fruits – oranges, grapefruits, etc.).
an older man drinking water and looking concerned
  • Drink more liquids. Urinating more frequently flushes bacteria out of the body.
  • Take warm baths (sitz baths).
  • Use a heating pad or a hot water bottle.
  • Try to relax and take it easy. A doctor might recommend relaxation exercises.


Resources

BJU International

Rees, Jon, et al.
“Diagnosis and treatment of chronic bacterial prostatitis and chronic prostatitis/chronic pelvic pain syndrome: a consensus guideline”
(First published: February 24, 2015)
https://bjui-journals.onlinelibrary.wiley.com/doi/full/10.1111/bju.13101

FamilyDoctor.org (American Academy of Family Physicians)

“Prostatitis”
(Last updated: April 24, 2020)
https://familydoctor.org/condition/prostatitis/

Mayo Clinic

“Prostatitis”
(February 19, 2022)
https://www.mayoclinic.org/diseases-conditions/prostatitis/symptoms-causes/syc-20355766

Medical News Today

Newman, Tim
“What is the prostate gland?”
(Updated: November 15, 2021)
https://www.medicalnewstoday.com/articles/319859

National Institute of Diabetes and Digestive and Kidney Diseases

“Prostatitis: Inflammation of the Prostate”
(Last reviewed: July 2014)
https://www.niddk.nih.gov/health-information/urologic-diseases/prostate-problems/prostatitis-inflammation-prostate

Prostate Cancer and Prostatic Diseases

Polackwich, A. S. and D. A. Shoskes
“Chronic prostatitis/chronic pelvic pain syndrome: a review of evaluation and therapy”
(Published: March 8, 2016)
https://www.nature.com/articles/pcan20168

UpToDate

Meyrier, Alain MD and Thomas Fekete, MD
“Acute bacterial prostatitis”
(Topic last updated: October 25, 2021)
https://www.uptodate.com/contents/acute-bacterial-prostatitis

Meyrier, Alain MD and Thomas Fekete, MD
“Chronic bacterial prostatitis”
(Topic last updated: October 16, 2020)
https://www.uptodate.com/contents/chronic-bacterial-prostatitis

“Patient education: Bacterial prostatitis (The Basics)”
(Topic retrieved: January 8, 2022)
https://www.uptodate.com/contents/bacterial-prostatitis-the-basics

“Patient education: Chronic prostatitis and chronic pelvic pain syndrome (The Basics)”
(Topic retrieved: January 8, 2022)
https://www.uptodate.com/contents/chronic-prostatitis-and-chronic-pelvic-pain-syndrome-the-basics

Pontari, Michel, MD
“Chronic prostatitis and chronic pelvic pain syndrome”
(Topic last updated: September 10, 2021)
https://www.uptodate.com/contents/chronic-prostatitis-and-chronic-pelvic-pain-syndrome

Urology Care Foundation

“What is a Urine Culture Sample?”
https://www.urologyhealth.org/urology-a-z/u/urine-culture-sample

“What You Need to Know About Prostatitis”
(August 28, 2019)
https://www.urologyhealth.org/healthy-living/care-blog/2019/what-you-need-to-know-about-prostatitis

WebMD

“What’s a Urine Culture?”
(Medically reviewed: November 30, 2021)
https://www.webmd.com/a-to-z-guides/what-is-urine-culture